Asymmetric dimethylarginine.
Research-backed amino acid with potential health benefits. Blocks nitric oxide production. Think of nitric oxide as the stuff that tells your arteries to relax and widen. ADMA does the opposite, making them stiff and narrow.
Reviewed March 2026
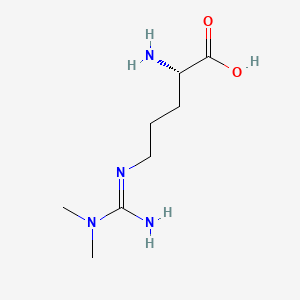 Amino acid
- Category
- Amino acid
What Asymmetric Dimethylarginine is, and what it does.
- Does it work
- No. As a supplement? Absolutely not. As something to get tested for if you have cardiovascular concerns? Maybe. Discuss with your doctor.
- How much to take
- Zero. None. You actively want less of this in your body. This isn't a supplement you buy.
- Time to feel it
- There is nothing to time here. Your body makes and clears it continuously, and it shows up only as a number on a laboratory panel, usually next to arginine.
- The first dose
- Nothing. It's a long-term indicator of endothelial health, not something that changes day-to-day.
- How well tolerated
- Unsafe to ingest. It's an endogenous toxin your kidneys work hard to clear. Don't add to their workload.
- How it feels
- You don't feel the compound itself. You feel the slow decline in circulatory health it causes over time. It's a background process.
- The overlooked benefit
- Homocysteine blocks the enzyme that clears it, which ties this molecule to folate, B12 and betaine status rather than to how much arginine you eat.
100 to 300mg a day is where Asymmetric Dimethylarginine works.
Source: Cardiovascular biomarker research; not a supplement ingredient
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
Asymmetric Dimethylarginine is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.
- marker of endothelial functionCohort study
- index of nitric oxide availability when read against arginineNarrative review
2 more claims
- enzymatic clearance by dimethylarginine dimethylaminohydrolaseIn vitro study
- association with markers of oxidative stressCohort study
Questions people ask about Asymmetric Dimethylarginine.
- So I should not take this supplement?
- Correct. Do not take it. Think of it like cholesterol or homocysteine—a number you want to keep in a healthy range, not something you eat.
5 more questions
- How do I lower my ADMA levels?
- Diet, exercise, and stress management. Supplements like L-Citrulline, L-Arginine, and antioxidants may help, but talk to your doctor first.
- How do I know if my levels are high?
- You need a specific blood test. It's not part of a standard panel. A functional medicine or preventative cardiology doctor can order it.
- What causes high ADMA?
- A mix of genetics, poor diet (especially low in antioxidants), smoking, lack of exercise, and conditions like kidney disease or insulin resistance.
- Is this related to L-Arginine?
- Yes. It's made from arginine in your body and it directly blocks the enzyme that uses arginine to create nitric oxide. They are opponents.
- Will my regular doctor test for this?
- Probably not, unless you're seeing a specialist for kidney or heart issues. It's more common in preventative and functional medicine.
Why these belong in the same formula, 24 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
ADMA is a competitive inhibitor at nitric oxide synthase, occupying the site arginine binds. Raising arginine shifts the ratio back toward normal nitric oxide output.
Citrulline escapes first-pass arginase and is recycled to arginine in the kidney and endothelium, raising the local arginine to ADMA ratio more reliably than oral arginine. It works on the same competition from upstream.
The citrulline portion regenerates arginine and lifts the arginine to ADMA ratio at the enzyme. The malate portion feeds the citric acid cycle and does not act on this competition.
The hydrochloride salt delivers the same arginine that competes with ADMA at nitric oxide synthase. The counter-ion changes solubility, not the mechanism.
ADMA is produced when arginine residues are methylated and is cleared largely by DDAH, whose activity is sensitive to the homocysteine and methylation state. Folate status shapes both ends of that balance.
Dietary nitrate is reduced to nitrite and then to nitric oxide without passing through nitric oxide synthase at all. That route is untouched by ADMA competition at the enzyme.
Betaine donates a methyl group to remethylate homocysteine back to methionine. Homocysteine inhibits the enzyme DDAH that clears ADMA, so anything that lowers homocysteine sits upstream of ADMA clearance. The chemistry is established. Whether a betaine dose moves a person's ADMA is a separate question that the candidate papers here do not answer.
Trimethylglycine feeds the betaine homocysteine methyltransferase route, which is one of two ways the body disposes of homocysteine. Because homocysteine inhibits DDAH, the enzyme that degrades ADMA, this route touches ADMA handling indirectly. It is an upstream mechanistic link rather than a measured effect on the marker.
Methionine synthase requires methylcobalamin to transfer a methyl group from 5-methyltetrahydrofolate to homocysteine. Without adequate B12 the folate route stalls and homocysteine rises. Since homocysteine inhibits ADMA clearance by DDAH, B12 status sits two steps upstream of this marker.
Cystathionine beta-synthase and cystathionine gamma-lyase both require pyridoxal 5-phosphate, and together they route homocysteine irreversibly to cysteine. That is the disposal arm rather than the recycling arm of the pathway. Its relevance here is the same indirect link through homocysteine and DDAH activity.
Methionine is converted to S-adenosylmethionine, the methyl donor that protein arginine methyltransferases use to methylate arginine residues in proteins. Proteolysis of those methylated proteins is what releases free ADMA. So methionine sits upstream of ADMA production, not of its clearance, which is the opposite direction from the B vitamins.
S-adenosylmethionine is the methyl donor PRMT enzymes use when they methylate arginine residues, the reaction that ultimately generates ADMA when those proteins are broken down. This means the methylation supply side and the clearance side of ADMA respond to different inputs. Worth stating plainly because it is easy to assume every methylation-supporting nutrient pushes the marker the same way.
Choline is oxidised to betaine, which then donates a methyl group in homocysteine remethylation. That places choline on the same route as betaine, one step earlier. The connection to ADMA runs through homocysteine and DDAH and is mechanistic rather than measured.
DDAH, the enzyme that degrades ADMA to citrulline and dimethylamine, carries an active site cysteine that is sensitive to oxidative modification. Thiol availability affects how much of the enzyme stays in its active form. N-acetylcysteine supplies cysteine for glutathione synthesis, which is the reasoning behind the pairing. The step from that to a measured ADMA change has not been shown in the papers available here.
Oxidative modification of the DDAH active site cysteine reduces its activity, and glutathione is the main intracellular buffer against that modification. This is why oxidative stress and ADMA are frequently reported together. The relationship is mechanistic and observational, not a demonstrated effect of a glutathione dose on the marker.
Dihydrolipoate regenerates other antioxidants and supports the intracellular thiol pool that keeps thiol-dependent enzymes active. DDAH is one such enzyme. The link is indirect and no candidate paper here measures the pairing.
Nitric oxide synthase needs tetrahydrobiopterin as a cofactor, and ascorbate helps keep that cofactor in its reduced form. ADMA acts on the same enzyme from the other side, competing with arginine at the substrate site. The two therefore touch NOS function by different routes. A supplementation study of L-arginine plus vitamin C in adults recovering from a viral illness reported on arginine pathway metabolites including ADMA.
A vitamin D supplementation study in ultramarathon runners reported changes in serum amino acid profiles, including methylarginine measures, around the exercise bout. What is measured is a circulating marker panel, not a performance or vascular outcome. Endurance exercise itself moves these values, so attributing a shift to the supplement alone would overstate the finding.
Long chain omega-3 fatty acids have been reported to influence endothelial function measures such as flow-mediated dilation, which is the same functional readout that ADMA is used to explain. The two connect at the level of the endothelium rather than by a shared enzyme. Flow-mediated dilation is a physiological marker, not a clinical outcome.
Garlic preparations have been reported to influence nitric oxide related endpoints in small human studies. ADMA is a competitive inhibitor of the enzyme that makes nitric oxide, so the two sit on the same pathway from different directions. The supporting work is small and the endpoints are markers.
Pine bark polyphenols have been studied for effects on endothelial nitric oxide availability. That is the same output that ADMA restricts by competing with arginine at NOS. The relationship is pathway-level and the human evidence base is small.
Taurine has been examined for effects on endothelial function markers in small trials. It does not act on ADMA metabolism directly and no shared enzyme links them. Included as a pathway-adjacent partner rather than a mechanistic one.
Arginase converts arginine to ornithine and urea, competing with nitric oxide synthase for the same substrate. ADMA restricts the NOS arm from the other side by competitive inhibition. Together they describe why the arginine to ADMA ratio, rather than either value alone, is what gets reported.
Lysine, arginine and the methylarginines all move on the y+ cationic amino acid transporter system. A large lysine load competes for that carrier. This is established transport biochemistry and it is one reason cellular arginine availability does not track plasma arginine exactly.
Nothing specific on file for Asymmetric Dimethylarginine. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Asymmetric Dimethylarginine actually does.
It is made by adding methyl groups to arginine inside proteins, and it only appears free in the blood when those proteins are recycled.
3 more mechanisms
It sits in the same slot on the enzyme that arginine uses, so what matters is the balance between the two, not either number alone.
An enzyme called DDAH breaks most of it down, and the kidneys clear the rest.
There is a mirror-image version, SDMA, that behaves differently, and confusing the two misreads the result.
The essence, in one line each.
- In a cross-sectional study of 50 adults with a diagnosed neurological condition, higher levels of asymmetric dimethylarginine were associated with thicker carotid artery walls.Cross-sectional study, in patients with MS. Mungan U et al., 2026 (Medicine). PMID 42071801 ↗
4 more findings
- In a cross-sectional study in 52 adults with a diagnosed kidney condition, higher levels of ADMA were associated with higher levels of NT-proBNP, a marker of heart strain.Cross-sectional study, in CKD patients. Hoxha E et al., 2025 (Cureus). PMID 41450363 ↗
- A review appraising the proposed role of ADMA in endothelial impairment during pregnancy with a raised blood pressure course and concurrent chronic infection. A review of proposed mechanisms rather than new data.Narrative review, in women with preeclampsia comorbid with HIV infection. Mthembu MH et al., 2026 (Frontiers in Medicine). PMID 42180710 ↗
- A systematic review of arginine, transsulfuration and folate pathway metabolomics in adults with chronic airway limitation, in which ADMA appears among the metabolites reviewed.Systematic review. Zinellu A et al., 2023 (Cells). PMID 37681911 ↗
- In a study of 155 hospitalized adults with a diagnosed respiratory infection, higher levels at admission were an independent predictor of a worse prognosis.Cohort study, in adult patients with confirmed SARS-CoV-2 infection. Eleuteri D et al., 2026 (Intensive Care Medicine Experimental). PMID 41663785 ↗
Chosen from the 14 we read for Asymmetric Dimethylarginine.
The studies, linked.
8 sources behind our Asymmetric Dimethylarginine verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Clinical trialContribution of Homocysteine and Asymmetric Dimethylarginine to Atherosclerosis and Cardiovascular Events in Maintenance Hemodialysis PatientsClinicalTrials.gov ↗200 participants, Completed
7 more linked trials
- Clinical trialPotential Effect for the Smoking on Periodontitis From the Perspective of Arginine Metabolites Symmetric Dimethylarginine (SDMA) and Asymmetric Dimethylarginine (ADMA)ClinicalTrials.gov ↗80 participants, Completed
- Clinical trialMethylation Biosignature in Childhood Chronic Kidney Disease: the Link Among Asymmetric Dimethylarginine, Homocysteine, and Cardiovascular DiseaseClinicalTrials.gov ↗69 participants, Completed
- Clinical trialPhase 4 Study of Effect of Testosteron Replacement Treatment on the Fibroblast Growth Factor-23, Asymmetric Dimethylarginine and Vitamin D Levels in the Congenital Hypogonadotropic HypogonadismClinicalTrials.gov ↗Phase 4, 49 participants, Completed
- Clinical trialPioglitazone and Serum Asymmetric Dimethylarginine (ADMA) in Patients With DiabetesClinicalTrials.gov ↗Phase 4, 36 participants, Completed
- Clinical trialValidation of the Dosage of Asymmetric Dimethylarginine (ADMA) Plasma in the Assessment of Endothelial Dysfunction During Growth Hormone Deficiency and Intrauterine Growth RetardationClinicalTrials.gov ↗23 participants, Completed
- StudyPlasma homoarginine, arginine, asymmetric dimethylarginine and total homocysteine interrelationships in rheumatoid arthritis, coronary artery disease and peripheral artery occlusion diseasePubMed ↗Amino Acids, 2015, cited 27 times
- StudyReduction in asymmetric dimethylarginine plasma levels by coenzyme Q10 supplementation in patients with type 2 diabetes mellitus.PubMed ↗Minerva endocrinologica, 2015, cited 26 times
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.