Ingredients/Vitamin/Retinol

Retinol.

The time machine. Speeds up skin cell turnover and boosts collagen production. This reduces fine lines, fades dark spots, and smooths out texture.

StrongResearch strength0.1mcgDaily amount

Reviewed March 2026

Vitamin
RetinolIngredientMD
Category
Vitamin
Also filed under
Anti AgingSkinProven

What Retinol is, and what it does.

Does it work
Yes. It's the most studied and effective anti-aging ingredient available over-the-counter. This actually works.
How much to take
Topical use. Start with a low concentration, 0.25%-0.3%, 2-3 nights a week. Slowly work up to nightly use, then consider 0.5% or 1.0% if tolerated.
Time to feel it
Texture and tone changes read at eight to twelve weeks and keep improving for months. Early dryness, when it happens, settles inside the first two to three weeks.
The first dose
Probably nothing. The irritation, if any, usually starts after a few applications, not the first night.
With regular use
Visible reduction in fine lines, more even skin tone, smoother texture, and fewer breakouts. The real magic happens after 3-6 months of consistent use.
How well tolerated
Well tolerated for topical use, but irritation is common at first. Absolutely avoid if pregnant. Sunscreen is mandatory—your skin will be more sensitive.
How it feels
Initially, it can feel irritating. Dry, tight, flaky. After your skin adapts, you don't feel it working. You just see the results in the mirror over months.
The overlooked benefit
Plasma retinol stays flat across a wide range of intakes because the liver releases it on demand, so a normal blood level tells you little about how full your stores are.

How common this is.

Public health figures for this ingredient, reported by the agencies that publish them, cited and dated.

United States

AdultsNHANES 2005 to 2016

About 45% of US adults

take in less vitamin A than the estimated average requirement.

Reider et al., Nutrients 2020, immune-nutrient intakes in US adults, NHANES 2005 to 2016. ↗
5 more figures for United States
Men aged 19 and over, WWEIA NHANES 2013 to 2016

About 50% of US men aged 19 and over

take in less vitamin A from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 16 (vitamin A as retinol activity equivalents), males 19+: 50% below EAR (SE 1.3). ↗
Men aged 19 to 30, WWEIA NHANES 2013 to 2016

About 53% of US men aged 19 to 30

take in less vitamin A from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 16 (vitamin A as retinol activity equivalents), males 19-30: 53% below EAR (SE 3.0). ↗
Women aged 19 and over, WWEIA NHANES 2013 to 2016

About 41% of US women aged 19 and over

take in less vitamin A from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 16 (vitamin A as retinol activity equivalents), females 19+: 41% below EAR (SE 1.7). ↗
Girls aged 14 to 18, WWEIA NHANES 2013 to 2016

About 52% of US girls aged 14 to 18

take in less vitamin A from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 16 (vitamin A as retinol activity equivalents), females 14-18: 52% below EAR (SE 5.1). ↗
Adults, WWEIA NHANES 2013 to 2016

About 13% of US boys and 12% of US girls aged 1 to 3

take in more preformed retinol from food and drink than the tolerable upper intake level.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 17 (retinol), ages 1-3 against a UL of 600 micrograms: males 13% (SE 2.2), females 12% (SE 3.2) above UL. ↗

United Kingdom

Men aged 19 to 64NDNS 2012/13 to 2013/14

11% of UK men aged 19 to 64

take in less vitamin A from food than the lower reference nutrient intake.

National Diet and Nutrition Survey: Results from Years 5 and 6 (combined) of the Rolling Programme (2012/13-2013/14), Table E 'Average daily intake... for selected micronutrients', Vitamin A row, p.18 ↗NDNS Rolling Programme Years 5 and 6 combined, fieldwork 2012/13 to 2013/14
3 more figures for United Kingdom

Canada

Men aged 19 and overCCHS 2015

About 45% of Canadian men aged 19 and over

take in less vitamin A from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Vitamin A (mcg/d (RAE)), Male, 19 years and over ↗
3 more figures for Canada
Men aged 19 to 30, CCHS 2015

About 45% of Canadian men aged 19 to 30

take in less vitamin A from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Vitamin A (mcg/d (RAE)), Male, 19-30 years ↗
Women aged 19 and over, CCHS 2015

About 38% of Canadian women aged 19 and over

take in less vitamin A from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Vitamin A (mcg/d (RAE)), Female, 19 years and over ↗
Girls aged 14 to 18, CCHS 2015

About 35% of Canadian girls aged 14 to 18

take in less vitamin A from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Vitamin A (mcg/d (RAE)), Female, 14-18 years ↗

Australia

AdultsNNPAS 2023 to 2024

About 1 in 5 Australians

aged 2 and over take in less vitamin A than the estimated average requirement.

ABS, Usual nutrient intakes, 2023, Vitamin A section ↗
4 more figures for Australia
Men aged 18 and over, NNPAS 2023 to 2024

Nearly 3 in 10 Australian men aged 18 and over

take in less vitamin A from food and drink than the estimated average requirement.

ABS, Usual nutrient intakes, 2023, Vitamin A section ↗
Men aged 18 to 29, NNPAS 2023 to 2024

About 42.9% of Australian men aged 18 to 29

take in less vitamin A from food and drink than the estimated average requirement.

ABS, Usual nutrient intakes, 2023, Vitamin A, Table: Proportion of people with an inadequate vitamin A intake by age and sex ↗
Women aged 18 and over, NNPAS 2023 to 2024

About 1 in 5 Australian women aged 18 and over

take in less vitamin A from food and drink than the estimated average requirement.

ABS, Usual nutrient intakes, 2023, Vitamin A section ↗
Girls aged 12 to 17, NNPAS 2023 to 2024

About 28.5% of Australian girls aged 12 to 17

take in less vitamin A from food and drink than the estimated average requirement.

ABS, Usual nutrient intakes, 2023, Vitamin A, Table: Proportion of people with an inadequate vitamin A intake by age and sex ↗

Population figures from public health data. Context for the category, not a statement about any individual and not a claim about this product.

0.1mcg a day is where Retinol works.

How much to take a dayHigh confidence
0.1mcg
Daily maintenanceThe everyday amount, and where most daily supplements sit. This is the one you take month after month.
3,000mcgClinical territory. Trials run high on purpose, for a set number of weeks, against one measured outcome. Impressive to hit, and not what a daily product is for.
Above 3,000mcgPast what the research covers. More capsules rather than more effect.
MORE EFFECT ↑0900mcg3,000mcg plateauDAILY DOSE →
The shaded band is where the dosing trials landed.

Source: NIH ODS + Ross 2006 review

The proof, claim by claim.

What these words mean

These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.

Extensively studied.

The absolute gold standard of dermatology.

  • Reduces fine lines and wrinkles via collagen stimulationMultiple RCTs and In-vivo Biopsy Studies
  • Improves skin texture and hyperpigmentationRandomized, double-blind, vehicle-controlled trials
1 more claim
  • Increases epidermal thicknessComparative human clinical studies

Questions people ask about Retinol.

Will it make my skin peel?
Probably, at first. It's a sign it's working by speeding up cell turnover. Start slow and moisturize well to manage it.
5 more questions
How long until I see results?
Patience is key. You might see texture improvements in 4-6 weeks, but real wrinkle reduction takes 3-6 months of consistency.
Can I use it with Vitamin C?
Yes, but not at the same time. Use Vitamin C in the morning and Retinol at night to avoid irritation and deactivation.
Is a higher percentage always better?
No. A 1.0% isn't better than a 0.5% if it just irritates your skin. Consistency with a strength you can tolerate beats high-strength inconsistency.
What's the difference between retinol and tretinoin?
Tretinoin (Retin-A) is the prescription-strength version. It's more powerful, but also much more irritating. Retinol is the strongest you can get over the counter.
Do I need to use it forever?
If you want to maintain the results, pretty much. Think of it as long-term maintenance for your skin.
Pairs well with33 on file
Retinol + Niacinamide (Vitamin B3)Established barrier biochemistry
Retinol + Hyaluronic AcidEstablished humectant chemistry
Retinol + CeramidesBarrier-lipid biology
Retinol + Zinccofactor and transport protein
Retinol + Vitamin Eoxidation control
Retinol + Beta Caroteneprecursor-product pair
Why these belong in the same formula, 33 pairings

Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.

Retinol + Niacinamide (Vitamin B3)Established barrier biochemistry

Niacinamide drives the skin's production of barrier lipids and reduces the water it loses through the outer layer, which buffers the dryness and stinging that retinol's faster cell turnover tends to bring. The two commonly share a formula because niacinamide steadies the same barrier retinol is working on.

Retinol + Hyaluronic AcidEstablished humectant chemistry

Hyaluronic acid binds many times its weight in water and holds it in the upper skin layers, offsetting the dryness and flaking retinol often causes as it speeds cell renewal. It keeps the skin hydrated while retinol works on turnover.

Retinol + CeramidesBarrier-lipid biology

Ceramides are the main lipids that seal the outer skin and keep moisture in, so replenishing them supports the barrier while retinol's quicker turnover can leave it briefly more permeable and dry. They restore the same lipid class the barrier is built from.

Retinol + Zinccofactor and transport protein

Zinc is needed to make retinol binding protein and is the metal in the retinol dehydrogenase enzymes that convert retinol to retinal. Low zinc limits how much retinol can be mobilised and used.

Retinol + Vitamin Eoxidation control

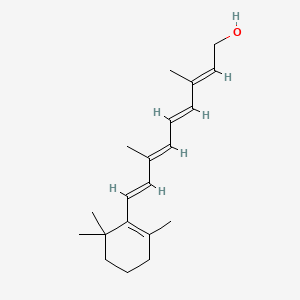
Retinol's polyene chain oxidises readily, and tocopherol is the standard lipid-phase antioxidant used to keep it intact in oils and creams. Tocopherol also spares retinol from oxidation in tissue lipids.

Retinol + Beta Caroteneprecursor-product pair

Beta-carotene is cleaved by BCO1 into retinal and then retinol, so it is the provitamin form of the same molecule. When preformed retinol intake is already high, conversion from carotene is downregulated, which is why total vitamin A activity is counted across both.

Retinol + Vitamin Aadditive intake of the same activity

Retinol is the alcohol form of preformed vitamin A, so a formula carrying both is stacking one nutrient twice. Total retinol activity equivalents are what matter, not the two label lines.

Retinol + Ironnutrient interaction

Vitamin A status influences how iron is released from stores and taken up for red cell production, so retinol adequacy supports iron use. The pairing is well described in nutrition science.

Retinol + Vitamin D3competition at a shared receptor partner

Retinoic acid receptors and the vitamin D receptor both pair with RXR to bind DNA, so a large retinoid load can occupy the shared partner and blunt vitamin D signalling. Balanced dosing keeps the two nuclear signals from crowding each other.

Retinol + Squalaneformulation practice

Squalane is an occlusive emollient that reduces water loss through the outer skin layer, which is the layer retinol perturbs while cells adjust. Layering it is standard practice with retinoid routines.

Retinol + Glycolic Acidadditive barrier stress

Both loosen the outer skin layer, glycolic acid by weakening corneocyte adhesion and retinol by speeding cell turnover. Applied together the barrier stress compounds, which is why they are usually alternated.

Retinol + Salicylic Acidadditive barrier stress

Salicylic acid dissolves lipid plugs and thins the outer layer while retinol accelerates turnover of the same layer. Combining them at full strength raises dryness and tightness, so they are separated.

Retinol + Bakuchiolformulation practice

Bakuchiol produces retinoid-like changes in gene expression without being a retinoid, so it is used on alternate nights or in the same routine at lower retinol strength. The overlap is functional rather than chemical.

Retinol + Vitamin Ccomplementary collagen pathways

Ascorbate is the cofactor for the hydroxylases that mature collagen, while retinol raises the transcription of collagen genes. Both are needed for the same output, though their formulation pH differs enough that they are usually applied at separate times.

Retinol + MCT oilRetinol is fat-soluble and requires micellar solubilisation for uptake. Established absorption physiology, though medium-chain triglycerides specifically are not the vehicle used in most published absorption work.

Retinol and its esters cross the enterocyte only after they have been packaged into bile-salt micelles, which needs lipid in the lumen. A low-fat dose of a fat-soluble vitamin absorbs less completely than the same dose taken with fat. MCT provides that lipid, although medium-chain triglycerides are absorbed differently from long-chain fat and are not the vehicle used in most published absorption work.

Retinol + LecithinPhospholipid emulsifiers assist micelle formation. Established formulation and absorption chemistry.

Lecithin lowers interfacial tension and helps disperse a fat-soluble vitamin into fine droplets, which is why it appears in so many oil-based softgels. The effect is on the dispersion step that precedes absorption. It changes how much of a dose is presented for uptake, which is not the same as changing vitamin A status.

Retinol + PhosphatidylcholineSame phospholipid emulsification mechanism as lecithin, with a defined single species.

Phosphatidylcholine is the phospholipid that does most of the emulsifying work in lecithin, and it participates in the chylomicron assembly that carries newly absorbed retinyl esters out of the enterocyte. That places it on both sides of the absorption step. The mechanism is established. A measured increase in retinol uptake from adding it is not.

Retinol + Ox bileBile salts are structurally required for micelle formation. Established physiology.

Without bile salts, fat-soluble vitamins do not form the mixed micelles that deliver them to the brush border. That is why people with reduced bile flow absorb them poorly. Supplemental ox bile is used in that context, and the rationale is the missing solubilising agent rather than any action on retinol itself. Anyone in that situation should be working with a clinician.

Retinol + Digestive enzymesRetinyl esters require esterase hydrolysis before uptake. Established enzymology.

Supplements usually supply vitamin A as retinyl palmitate or acetate, and pancreatic carboxyl ester lipase plus brush border enzymes cleave the ester before the free retinol is absorbed. Where pancreatic output is low, that step is the bottleneck. An enzyme blend containing lipase addresses the hydrolysis step, not the vitamin.

Retinol + Fish OilLiver-derived fish oils carry preformed retinol. Established food and supplement composition. Flagged as cumulative intake.

Cod and other fish liver oils contain preformed vitamin A alongside their omega-3 fatty acids, while refined body-oil concentrates generally do not. Someone taking a liver oil plus a retinol supplement is adding two preformed sources. Because retinol accumulates in the liver and authorities publish upper intake levels for it, that total is worth totting up rather than assuming each product stands alone.

Retinol + LuteinCarotenoids and retinol share micellar and lipoprotein transport. Competition at that step is established, magnitude varies.

Fat-soluble micronutrients taken in one dose compete for space in the same mixed micelles and for the same lipoprotein carriers out of the enterocyte. High single doses of one carotenoid can lower the absorption of another measured in the same meal. That is an absorption measurement, not a status outcome, and separating doses across the day is the usual practical response.

Retinol + LycopeneSame shared micellar transport step. Documented interactions between carotenoids at high single doses.

Lycopene is highly lipophilic and loads into the same micelles that carry retinol and other carotenoids. Competition shows up in absorption studies where one is given at a large single dose. Whether that translates into any change in vitamin A status at ordinary supplemental amounts has not been shown.

Retinol + AstaxanthinShared lipid transport route. Interaction inferred from carotenoid absorption work rather than measured with retinol.

Astaxanthin travels the same micelle and chylomicron route as other fat-soluble pigments. Competition is plausible on that basis and has not been measured against retinol specifically. Confidence stays Early for that reason.

Retinol + Beta-sitosterolPlant sterols reduce absorption of fat-soluble micronutrients from the same micelles. Established mechanism, effect sizes vary by nutrient.

Plant sterols displace other lipophilic compounds from mixed micelles, which is how they lower cholesterol absorption and also why carotenoid concentrations tend to fall in people using sterol-enriched products. Preformed retinol appears less affected than the carotenoids, and the mechanism reaches the same micelle. Separating a sterol product from a fat-soluble vitamin dose is the practical response.

Retinol + Activated charcoalNon-selective luminal adsorption. Established pharmacology of adsorbents.

Activated charcoal binds organic molecules in the gut without discriminating, which includes fat-soluble vitamins taken at the same time. Nothing about retinol makes it exempt. If both are used, spacing them by several hours is the standard way to keep the adsorbent from taking the vitamin with it.

Retinol + Vitamin K2 (MK-7)Retinoid and vitamin K signalling both intersect with bone mineral handling. The receptor-level link for retinoids is established, the combined effect is not.

Retinoic acid regulates osteoblast and osteoclast gene expression through RAR, and vitamin K2 is the cofactor for carboxylating osteocalcin and matrix Gla protein. Both therefore touch bone mineral handling by separate routes. High preformed vitamin A intake has been associated with lower bone density in observational work, which is an association and not a cause. The pairing is worth naming as a modulating relationship, not as a benefit.

Retinol + IodineVitamin A status influences thyroid hormone signalling through RXR heterodimers. Mechanistic and observational, not a combination trial.

Retinoic acid receptors partner with RXR, and RXR also heterodimerises with the thyroid hormone receptor, which puts retinoid and thyroid signalling on a shared partner. Observational work in populations with low vitamin A status reports altered thyroid markers alongside iodine status. Those are markers and associations. The takeaway is that the two nutrients are not independent, not that one corrects the other.

Retinol + Vitamin B2 (Riboflavin)Riboflavin status affects retinol mobilisation from liver stores in animal work. Mechanistic and non-human.

Flavin-dependent enzymes participate in retinol handling, and animal work has reported impaired mobilisation of hepatic retinol under riboflavin restriction. Human data on this pairing are sparse. It is a mechanistic dependency worth stating, measured mainly outside people.

Retinol + Whey protein isolateRetinol travels bound to retinol-binding protein, whose synthesis depends on protein and zinc status. Established physiology.

Plasma retinol does not circulate free. It rides on retinol-binding protein 4, a liver-made protein. Where protein intake is low, RBP synthesis falls and plasma retinol can look low even when liver stores are not empty. Adequate dietary protein is therefore part of retinol transport rather than a separate topic. Adding whey to an already adequate protein intake is not expected to change anything here.

Retinol + Vitamin E mixed tocopherolsStandard formulation antioxidant practice for a light and oxygen sensitive vitamin. Established chemistry.

Retinol has a conjugated polyene chain that oxidises readily on exposure to air, light and heat, which is why manufacturers add tocopherols or ascorbyl palmitate to the oil or beadlet matrix. The tocopherol is protecting label potency in the container. That is a stability function and says nothing about what either nutrient does after absorption.

Retinol + Collagen PeptidesRetinoic acid regulates collagen gene expression in skin. The transcriptional link is established, the combination is untested.

Retinoic acid signalling through RAR alters procollagen and matrix metalloproteinase expression in skin fibroblasts, and collagen peptides supply the amino acids and peptide fragments that show up in collagen studies. One acts on the instruction, the other on the raw material, which is the rationale offered for pairing them. No study located here tests the pair, so this sits at Early.

Retinol + L-prolineProline and hydroxyproline are structural residues of collagen. Established biochemistry, no combination evidence.

Collagen is rich in proline and hydroxyproline, and hydroxylation of proline residues is what stabilises the triple helix. Retinoid signalling changes how much collagen a fibroblast is instructed to make, not how much proline is available. Substrate and signal are different levers, and nothing here measures them together.

Retinol + Psyllium huskViscous fibre can slow lipid and fat-soluble micronutrient absorption from the same meal. Established physiology, small effect sizes.

A viscous gel slows lipid emulsification and diffusion to the brush border, which is one reason large fibre doses can reduce absorption of fat-soluble compounds taken at the same time. Reported effects are modest and mostly measured for carotenoids. Spacing a fibre dose from a fat-soluble vitamin dose is the practical answer.
Who should be cautious

Talk to a doctor before taking Retinol if any of these apply to you: Irritating initially. Do not use if pregnant, Pregnancy. These are flags to check first, not effects Retinol is known to cause.

Not medical advice. Show the label to your pharmacist.

What Retinol actually does.

Established

Retinol rides through the blood attached to two carrier proteins rather than floating loose.

3 more mechanisms
Established

The body converts retinol in two steps into retinoic acid, which is the form that switches genes on and off.

Established

Retinoic acid works by turning genes on, using a partner protein that vitamin D and thyroid hormone also use.

Established

Your eyes build their light-detecting pigment from a form of retinol, which is part of how normal vision in low light works.

More than one route, 7 steps on record

Where Retinol comes from.

Retinol is either built in a factory, concentrated out of fish liver oil, or supplied as carotene that your own gut converts. All three are sold by measured potency, and the route mainly decides whether a product can call itself plant-based.

What this route gives you

The same molecule is reached more than one way. Which route a given product used is a manufacturing choice, and the finished compound is the same either way.

7 steps on record
Starts as
Beta-ionone for the synthetic route, fish liver oil for the animal route, or carotenoid-bearing plant and algal material for the provitamin route

Beta-ionone is built from citral or acetone chemistry. Which feedstock a product uses decides whether the label can say vegetarian or vegan.

Converted by
C15 plus C5 coupling to the retinyl skeleton

In the industrial synthesis a fifteen-carbon fragment from beta-ionone is joined to a five-carbon unit, then isomerised to the all-trans configuration that the biology recognises.

Extracted by
Saponification and molecular distillation of fish liver oil

The animal route concentrates naturally occurring retinyl esters out of liver oil rather than building the molecule. Potency varies with the fish and the season.

Converted by
Esterification to acetate or palmitate

Most material is esterified because the free alcohol is too fragile to handle at scale. Cosmetic-grade retinol is kept as the alcohol and handled under nitrogen instead.

Purified by
Crystallisation or distillation, then dilution in oil

The concentrate is purified and then cut to a working potency in a carrier oil, which is what an assay is run against.

Standardised to
Potency assay in IU or retinol activity equivalents

Vitamin A is sold on assayed potency rather than on weight of material, and manufacturers add overage to allow for degradation across shelf life.

Ends up as
Oil dilution, antioxidant-protected beadlet, or a stabilised topical dispersion

The finished format is chosen for the matrix it has to survive: oil for softgels, beadlets for tablets and powders, encapsulated dispersions for skin products.

Labels usually give potency and the chemical form but not the manufacturing route, the overage added for shelf life, or which antioxidant protects the material in the container.

Getting Retinol from food.

The whole-food sources on file. A supplement closes the gap, it does not replace dinner.

Beef LiverSweet PotatoCarrots

A gram-for-gram figure (how much of each you would eat to match a dose) will appear here once it is sourced and reviewed. This page will not print a number it cannot cite.

The forms it comes in.

RetinolThe unesterified alcohol with a conjugated polyene chain. Sensitive to light, oxygen and heat, so it is handled under inert conditions and formulated with antioxidants.Fits Topical formats and any formulation that specifies the alcohol rather than an ester.Trade-off Degrades readily on exposure to air, light and warmth, so packaging, antioxidants and shelf-life testing carry more of the burden than with an ester.
4 more forms
Retinyl palmitateRetinol esterified to palmitic acid, which is also how the body stores it. Requires esterase hydrolysis in the gut before uptake, or in skin before conversion.Fits Oil-based oral supplements and cosmetic bases where stability in the container is the limiting problem.Trade-off The extra hydrolysis step means delivery depends on esterase activity, and the long fatty acid chain makes up a large share of the molecule's weight.
Retinyl acetateRetinol esterified to acetic acid. More stable than the free alcohol, and small enough to fit dry blends and multivitamin tablets after beadlet encapsulation.Fits Dry powder blends, tablets and fortified foods where an oil is impractical.Trade-off Still needs hydrolysis before uptake, and in a dry matrix its stability depends heavily on the encapsulation rather than on the molecule itself.
RetinaldehydeOne oxidation step closer to retinoic acid than retinol is, so it needs only a single enzymatic conversion in skin.Fits Topical formulations where the developer wants fewer conversion steps than the alcohol requires.Trade-off Less chemically stable and harder to formulate than the esters, and it discolours some bases.
Beadlet or encapsulated retinolRetinol or an ester dispersed in a gelatin, starch or modified-starch matrix with an antioxidant such as tocopherol or ascorbyl palmitate, then dried into free-flowing particles.Fits Multivitamin tablets, powders and fortified foods where the raw vitamin would not survive processing.Trade-off The matrix adds non-active weight and the declared potency depends on overage and on the beadlet holding up through compression and storage.Formulation aid
What the strongest studies found

The essence, in one line each.

  1. In a network meta-analysis of 23 trials in 3,905 people with sun-damaged skin, topical retinol significantly improved fine wrinkles and was among the agents that most improved skin hyperpigmentation.Network meta-analysis, in participants in trials for facial photoaging. Lin et al., 2025 (Scientific Reports). PMID 40707570 ↗
11 more findings
  1. In a 26-week trial in middle-aged Japanese women with mild sun damage, a 0.075% retinol cream applied nightly improved fine wrinkling in 50% of participants, versus 24% for the vehicle cream, and deep wrinkling in 28% versus 2%.Randomised trial. Kikuchi et al., 2009 (Journal of Dermatological Treatment). PMID 20078381 ↗
  2. In a 12-week randomised trial in people with facial sun damage, a daily retinol cream significantly decreased wrinkle surface area and hyperpigmentation, but users reported more skin scaling and stinging than with a comparator cream.Randomised trial, in patients with facial photoageing. Dhaliwal et al., 2018 (British Journal of Dermatology). PMID 29947134 ↗
  3. In a meta-analysis of trials in pregnant or breastfeeding women from low- and middle-income countries, vitamin A supplementation raised maternal blood vitamin A (standardised difference 0.60) and vitamin A in breast milk (0.53), while infant and cord blood levels showed no detectable change.Meta-analysis. Shinde et al., 2025 (Advances in Nutrition). PMID 40752545 ↗
  4. In 504 schoolchildren given 200,000 IU vitamin A twice over 11 months, with or without weekly iron, no detectable change was found in haemoglobin, iron markers or retinol-binding protein against placebo.Randomised trial. Gutema et al., 2026 (European Journal of Clinical Nutrition). PMID 41291212 ↗
  5. Across studies measuring vitamin A status in at-risk groups, the accuracy of routine blood markers such as retinol-binding protein varied by test and by population, so a single reading tracks status imperfectly.Systematic review. Gannon et al., 2025 (Cochrane Database of Systematic Reviews). PMID 40433851 ↗
  6. Measured serum retinol levels during oral retinol supplementation in very low birth weight preterm infants and reported on how effectively the oral route raised those levels. The outcome is a circulating status marker in a hospital population, not a general effect of retinol.Open-label trial, in VLBW preterm infants. Garofoli F et al., 2018 (International Journal of Immunopathology and Pharmacology). PMID 30897987 ↗
  7. Reviews how retinol circulates bound to retinol-binding protein in complex with transthyretin, which is what sets plasma retinol transport and clearance. A mechanistic review, so it grounds transport biochemistry rather than any supplementation outcome.Narrative review. Brown D et al., 2026 (Journal of Cardiovascular Development and Disease). PMID 42188091 ↗
  8. In a study of 684 children in India aged 4-18, differences in vitamin A status and body weight were not associated with a detectable difference in antibody responses after routine childhood vaccination. A failure to detect a difference, not evidence that no difference exists.Cohort study. Ratishvili T et al., 2026 (Vaccine). PMID 42229095 ↗
  9. Reviews how low vitamin A status arises, how clinicians recognise it, and where detection falls short in one tertiary referral setting. A clinical review of a nutrient status, describing recognition gaps rather than testing supplemental retinol.Narrative review. Fearon KH et al., 2026 (Nutrients). PMID 42075121 ↗
  10. Maternal liver retinol stores did not ensure adequate vitamin A status in calves when late-gestation intake was restricted. An animal study, and a demonstration that maternal stores are an imperfect predictor of offspring status rather than a human finding.Animal study. Speer HF et al., 2026 (Animal Science Journal). PMID 41964226 ↗
  11. Examined how vitamin A and zinc supplementation interact in finishing cattle, consistent with the known dependence of retinol transport and oxidation on zinc status. An animal study, so it grounds the interaction mechanism and not a human dose relationship.Animal study. Eekhoff MK et al., 2026 (Journal of Animal Science). PMID 42467838 ↗

Chosen from the 71,290 we read for Retinol.

Primary evidence

The studies, linked.

2 sources behind our Retinol verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.

  1. ReviewVitamin A, Cancer Treatment and Prevention: The New Role of Cellular Retinol Binding Proteins
    BioMed Research International, 2015, cited 131 times, open access
    PubMed ↗
1 more linked trial

From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.

Side effects reported to the FDA

Problems people have reported.

Read this carefully. These are 20,365 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Retinol is, not how risky it is. A report is not proof Retinol caused anything. It is a signal of what to watch for, nothing more.

Fatigue
640
Drug Ineffective
602
Nausea
583
3 more reported effects
Off Label Use
522
Pain
508
Diarrhoea
500

Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.

FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.