Vitamin B 12.
Research-backed vitamin with potential health benefits. Makes red blood cells, supports nerve health, and helps your body create energy from food. Your body can't produce it on its own.
Reviewed March 2026
 Vitamin
- Category
- Vitamin
What Vitamin B 12 is, and what it does.
- Does it work
- Yes. Especially for plant-based eaters and anyone over 50. The consequences of deficiency are severe and easily preventable.
- How much to take
- 1,000mcg
- Time to feel it
- Days to a few weeks in people who were running low. Methylmalonic acid responds within weeks, and red cell turnover takes two to three months.
- The first dose
- Nothing, unless you are severely deficient. This is not a stimulant. It works in the background.
- With regular use
- Steady energy, sharper thinking, and healthy nerve function. You're supporting normal function against slow changes you might not otherwise notice.
- How well tolerated
- Well tolerated. There is no established upper limit for B12. Your body is smart and just gets rid of what it doesn't use.
- How it feels
- If you were low: like a fog has lifted. If you weren't: no different. Think of it as an insurance policy, not a performance enhancer.
- The overlooked benefit
- It frees folate from its methyl-trapped form, which is why folate on its own can tidy one blood marker while the cobalamin-dependent step stays slow.
250 to 1,000mcg a day is where Vitamin B 12 works.
Source: NIH ODS + Allen 2009 B12 review
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
Vitamin B 12 is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.
- Vitamin B12 status on plant-based dietsMeta-analysis
- Homocysteine already in the normal rangeMeta-analysis
3 more claims
- Red blood cell formationNarrative review
- Nerve signalling supportRandomised trial
- Absorption of high oral doses by passive diffusionRandomised trial
Questions people ask about Vitamin B 12.
- Do I need this if I eat meat?
- Probably not, unless you're over 50 or have digestive issues. Stomach acid declines with age, making it harder to absorb from food.
3 more questions
- Will this give me an energy buzz?
- Nope. It helps your cells produce energy efficiently over time. It's a foundational repair, not a cup of coffee.
- Why do vegans need it?
- B12 is made by bacteria and is only found reliably in animal products. Plants don't make it, so supplementation is essential.
- What are the first signs of deficiency?
- Fatigue and brain fog are common. A pins-and-needles sensation in your hands or feet is a major red flag that you should see a doctor.
Why these belong in the same formula, 23 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
Methionine synthase needs methylcobalamin to move a methyl group from 5-methyltetrahydrofolate to homocysteine, so without B12 folate accumulates in that one methylated form and cannot re-enter the cycle. Folate alone can also mask the blood picture of low B12, which is why they are dosed together.
Methylfolate is the exact methyl donor that methionine synthase hands to cobalamin, so the two work as a unit at one enzyme. Supplying methylfolate without adequate B12 leaves the methyl group stuck.
B12 and folate remethylate homocysteine to methionine while pyridoxal 5-phosphate drives cystathionine beta-synthase, the route that sends it toward cysteine. Covering both keeps homocysteine moving in either direction.
Betaine homocysteine methyltransferase remethylates homocysteine using betaine instead of methylfolate and B12. The two routes back each other up, so the pair is standard in methylation formulas.
SAM-e gives up its methyl group and becomes homocysteine, which B12 and folate convert back to methionine and then to SAM-e again. Without the B12 step the cycle drains toward homocysteine.
Methylcobalamin serves methionine synthase in the cytosol while adenosylcobalamin serves methylmalonyl CoA mutase in the mitochondrion. A formula carrying both covers each enzyme without relying on interconversion.
The intrinsic factor and B12 complex binds its cubilin receptor in the ileum in a calcium dependent manner. Low ileal calcium slows that receptor mediated uptake step.
B12 supplies the one carbon units dividing red cell precursors need while iron is built into heme, so both must be present for normal red cell production. Low status in either shows up in the same blood indices.
Methionine synthase reductase, the flavoprotein that returns oxidised cobalamin to its active state, depends on FAD from riboflavin. Riboflavin status therefore affects how well the B12 in circulation actually functions.
Very high ascorbate concentrations can chemically degrade cobalamin, so large simultaneous doses are better separated. The effect is clearest in solution rather than in a dry tablet.
Cobalamin must be freed from food protein by pepsin and acid before intrinsic factor can bind it, so low stomach acid slows that release. Supplemental crystalline B12 bypasses much of this, which is why oral forms are less acid dependent.
Methionine synthase uses methylcobalamin to move a methyl group from 5-methyltetrahydrofolate onto homocysteine, regenerating methionine. Cobalamin availability therefore sets how much of the homocysteine pool is recycled by that route. This is settled enzymology. Homocysteine is a marker, not an outcome.
Choline is oxidised to betaine, which offers a second, folate-independent way to methylate homocysteine back to methionine. When cobalamin-dependent methionine synthase is running slowly, the betaine route carries more of the load. The two nutrients feed the same one-carbon pool from different directions.
Endogenous phosphatidylcholine synthesis by the PEMT route consumes three S-adenosylmethionine molecules per phosphatidylcholine made, drawing on the same methyl pool that cobalamin helps regenerate. Dietary phosphatidylcholine reduces demand on that route. The link is biochemical rather than a tested pairing.
Creatine synthesis is one of the largest single consumers of S-adenosylmethionine in the body, at the guanidinoacetate methyltransferase step. Supplemental creatine lowers how much endogenous synthesis is needed and so spares methyl groups whose regeneration depends on cobalamin and folate. Read it as methyl-pool arithmetic, not a measured combination effect.
Homocysteine has two fates: remethylation to methionine, which needs cobalamin, or transsulfuration to cystathionine and then cysteine, which needs vitamin B6. The two branches share a substrate, so the state of one shapes flux through the other. Supplying cysteine reduces the pull on that transsulfuration branch.
Cysteine produced from homocysteine by transsulfuration is the rate-limiting building block of glutathione. Cobalamin status shifts how much homocysteine goes down that branch rather than back to methionine. The relationship is mechanistic and measured as metabolite concentrations.
Taurine is made from cysteine, itself a downstream product of the transsulfuration branch that competes with cobalamin-dependent remethylation for homocysteine. The connection is real but several steps removed, so it is mechanistic context rather than a reason to dose the two together.
Adenosylcobalamin drives methylmalonyl-CoA mutase, the enzyme that converts propionyl-CoA derived from odd-chain fats and several amino acids into succinyl-CoA. Carnitine buffers surplus propionyl groups as propionylcarnitine when that step slows. Both sit on the same short-chain acyl handling route.
Propionyl-CoA carboxylase is a biotin enzyme and it feeds methylmalonyl-CoA straight into the adenosylcobalamin-dependent mutase step. The two cofactors sit one reaction apart on the same pathway, which is why organic acid profiles can look similar when either is short. Established biochemistry, no combination trial implied.
Food-bound B12 is attached to protein and has to be released by stomach acid and pepsin before it can bind haptocorrin and then intrinsic factor. Crystalline B12 in a supplement skips that step, which is why supplemental and food-bound forms behave differently in people with low gastric acid output. The dependency applies to the food-bound form specifically.
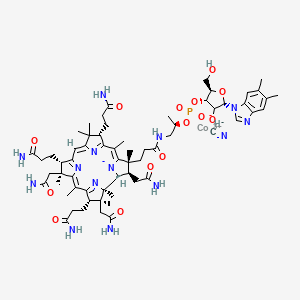
Cobalamin is built around a single cobalt ion held in a corrin ring. The metal is the reactive centre of both the methyl and adenosyl forms. Bacteria need cobalt in the fermentation medium to make the vitamin at all. Humans have no use for free cobalt as a nutrient, only for the assembled vitamin.
Activated charcoal adsorbs small molecules non-selectively in the gut lumen, so anything taken alongside it, including a water-soluble vitamin, can be bound and carried through. The interaction is generic to adsorbents rather than specific to cobalamin. Separating the two by several hours is the usual practice.
Nothing specific on file for Vitamin B 12. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Vitamin B 12 actually does.
Vitamin B12 is built around a central cobalt atom, making it the only vitamin with a metal at its reactive core.
3 more mechanisms
Your body uses B12 in exactly two enzymes, each needing a different active form of the vitamin, one in the main cell fluid and one inside the mitochondria.
One of those B12-dependent enzymes moves a methyl group from a folate form onto homocysteine, which both regenerates methionine and frees up folate to be used again.
Because B12 is what frees up trapped folate, low B12 and low folate can look similar on lab tests, and giving folate alone can normalize one marker while the B12-dependent step is still running slow underneath.
Getting Vitamin B 12 from food.
The whole-food sources on file. A supplement closes the gap, it does not replace dinner.
A gram-for-gram figure (how much of each you would eat to match a dose) will appear here once it is sourced and reviewed. This page will not print a number it cannot cite.
The forms it comes in.
4 more forms
The essence, in one line each.
- In a systematic review of 16 trials in children under 12, vitamin B12 supplementation reduced vitamin B12 deficiency and probably increased total vitamin B12 concentrations, but it may have little to no effect on growth, cognitive function, development, or measures of red blood cell health.Systematic review. Larvie et al., 2026 (Cochrane Database of Systematic Reviews). PMID 42227307 ↗
5 more findings
- In a randomised trial, daily vitamin B12 for one year did not have a statistically significant effect on the incidence of common infections in 600 infants aged 6-11 months who were at risk of deficiency.Randomised trial. Strand et al., 2026 (The Journal of Nutrition). PMID 41997492 ↗
- In a randomised trial, vitamin B12 supplementation during pregnancy had a negative effect on motor performance in infants aged 8 to 12 weeks.Randomised trial. Kvestad et al., 2026 (The Journal of Nutrition). PMID 41461260 ↗
- In a study of women in Tanzania, a supplement with high-dose vitamin B-12 taken during pregnancy increased vitamin B-12 in breast milk at 6 weeks after birth, and when taken after birth, it increased B-12 in breast milk at 7 months.Randomised trial. Wang et al., 2024 (The American Journal of Clinical Nutrition). PMID 38432714 ↗
- The trial did not detect a difference in neurophysiologic outcomes in the children of women given B12 during pregnancy and early lactation. A failure to detect a difference is not evidence that none exists.Randomised trial. Srinivasan et al., 2020 (The Journal of Nutrition). PMID 32470975 ↗
- A commentary discussing oral dosing of B12 in a further group of users, based on the passive absorption route that operates at high oral doses.Narrative review. Alpers, 2018 (The American Journal of Clinical Nutrition). PMID 29982312 ↗
Chosen from the 6 we read for Vitamin B 12.
The studies, linked.
12 sources behind our Vitamin B 12 verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Meta-analysisMeta-analysis reveals protective effects of vitamin B on stroke patientsPubMed ↗Translational Neuroscience, 2015, cited 13 times, open access
11 more linked trials
- PubMed ↗
- ReviewVitamin and mineral supplementation for preventing dementia or delaying cognitive decline in people with mild cognitive impairment.PubMed ↗The Cochrane database of systematic reviews, 2015, cited 133 times, open access
- ReviewScreening for Vitamin D Deficiency: A Systematic Review for the U.S. Preventive Services Task ForcePubMed ↗Annals of Internal Medicine, 2015, cited 125 times
- ReviewImpact of voluntary fortification and supplement use on dietary intakes and biomarker status of folate and vitamin B-12 in Irish adults.PubMed ↗The American journal of clinical nutrition, 2015, cited 76 times, open access
- ReviewVitamin C supplementation in pregnancy.PubMed ↗The Cochrane database of systematic reviews, 2015, cited 57 times, open access
- ReviewVitamin D for the treatment of respiratory diseases: is it the end or just the beginning?PubMed ↗The Journal of steroid biochemistry and molecular biology, 2015, cited 52 times
- ReviewB-vitamin status and bone mineral density and risk of lumbar osteoporosis in older females in the United States.PubMed ↗The American journal of clinical nutrition, 2015, cited 44 times, open access
- ReviewAcupuncture and vitamin B12 injection for Bell’s palsy: no high-quality evidence existsPubMed ↗Neural Regeneration Research, 2015, cited 22 times, open access
- StudySeasonal variations in serum 25-hydroxy vitamin D levels in a Swedish cohortPubMed ↗Endocrine, 2015, cited 182 times, open access
- StudyBrain atrophy in cognitively impaired elderly: the importance of long-chain ω-3 fatty acids and B vitamin status in a randomized controlled trial.PubMed ↗The American journal of clinical nutrition, 2015, cited 172 times, open access
- StudyEffects of vitamin D supplementation on intestinal permeability, cathelicidin and disease markers in Crohn’s disease: Results from a randomised double-blind placebo-controlled studyPubMed ↗United European Gastroenterology Journal, 2015, cited 163 times, open access
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 26,977 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Vitamin B 12 is, not how risky it is. A report is not proof Vitamin B 12 caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.