Vitamin K.
Research-backed vitamin with potential health benefits. Activates proteins that direct calcium to your bones and teeth. Also essential for normal blood clotting.
Reviewed July 2026
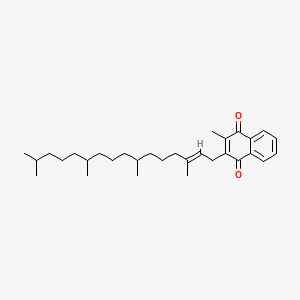 Vitamin
- Category
- Vitamin
What Vitamin K is, and what it does.
- Does it work
- Yes. Especially if you take high-dose Vitamin D. D3 increases calcium absorption, K2 makes sure it ends up in the right place.
- How much to take
- For the K2 form (MK-7), 100-200 mcg daily is the standard dose. Don't confuse mcg with mg.
- Time to feel it
- About four weeks of daily use.
- The first dose
- Zero. You won't notice a thing. This is a long game.
- With regular use
- The goal is healthier bones and clearer arteries over years. It's an investment in what you *don't* get: fractures and calcification.
- How well tolerated
- Well tolerated for the general population. The only major warning is for people on anticoagulant drugs like Warfarin.
- How it feels
- You don't feel it. It's like having a good accountant for your body's calcium budget – you just trust it's doing its job.
- The overlooked benefit
- Vitamin K is recycled rather than used up. The epoxide reductase loop regenerates each molecule many times, which is why a microgram-scale daily amount supports so much carboxylation.
90 to 120mcg a day is where Vitamin K works.
Source: NIH ODS
What the trial measured, in its words
A double-blind randomised dose-finding trial gave 60 postmenopausal women aged 50 to 69 either 0, 50, 100 or 200 micrograms of menaquinone-7 daily for four weeks on a controlled diet. The ratio of carboxylated to undercarboxylated osteocalcin rose dose dependently, with significant differences from the 0 microgram group at 100 and 200 micrograms. A companion 12-week trial in 120 people aged 20 to 69 confirmed the change at 100 micrograms daily. Both studies were run by authors affiliated with the R and D division of J-Oil Mills. An independent 8-week double-blind trial in 55 healthy prepubertal children found the same direction at 45 micrograms daily. What was measured is a blood marker of vitamin K status, not bone density and not a sensation.
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
Vitamin K is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.
- normal blood clotting functionNarrative review
- osteocalcin carboxylation statusRandomised trial
2 more claims
- bone mineral density maintenanceMeta-analysis
- matrix Gla protein activation and calcium handling in soft tissueRandomised trial
Questions people ask about Vitamin K.
- What's the difference between Vitamin K1 and K2?
- K1 is for blood clotting and comes from leafy greens. K2 is for calcium placement and comes from fermented foods and animal products. Supplements usually focus on K2.
5 more questions
- If I take Vitamin D, do I need K2?
- It's a very good idea. Vitamin D boosts calcium in your blood. K2 tells that calcium to go into your bones. They work as a team.
- What's better, MK-4 or MK-7?
- MK-7. It stays in your body much longer, so you only need to take it once a day. MK-4 is in and out in a few hours.
- Can I get enough from my diet?
- K1 is easy from salads. K2 is tough unless you eat a lot of natto (fermented soybeans) or certain hard cheeses. A supplement is more reliable for K2.
- Is it safe to take every day?
- Yes, for most people. The only major exception is if you're on a blood thinner like Warfarin. Then you must consult your doctor.
- Will this make my blood clot too much?
- No. For a healthy person, it just ensures your clotting system works normally. It won't create spontaneous clots.
Why these belong in the same formula, 25 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
Vitamin D increases the body's output of calcium-binding proteins such as osteocalcin, which stay inactive until vitamin K carboxylates them. The two work in sequence, one making the proteins and the other switching them on, to support normal calcium handling in bone.
Vitamin K activates osteocalcin and matrix Gla protein, the proteins that bind calcium and help steer it into the bone matrix and away from soft tissue. When vitamin K is low these proteins stay uncarboxylated and calcium is directed less precisely.
At high supplemental doses vitamin E and its quinone metabolite interfere with vitamin K-dependent carboxylation, which can blunt vitamin K's support of normal blood clotting. This is a recognized reason to keep large vitamin E doses and vitamin K in balance rather than stacking them heavily.
Phylloquinone clears fast and is used mainly in liver, while menaquinones circulate longer and reach bone and vessel wall. Carrying both covers hepatic and peripheral carboxylation from the same vitamin K cycle.
Phylloquinone is the vitamer that dominates hepatic carboxylation of the clotting factors and is partly converted to MK-4 in tissue. It is the liver-side half of total vitamin K activity.
MK-7 stays in circulation for days rather than hours, so it reaches extrahepatic Gla proteins that phylloquinone largely misses. It extends the same carboxylation function to bone and vascular tissue.
Magnesium is the cofactor for the hydroxylases that make active vitamin D, and active vitamin D drives transcription of the Gla proteins vitamin K carboxylates. The two nutrients sit at different points on one calcium-handling sequence.
Vitamin D raises transcription of osteocalcin and matrix Gla protein and raises calcium absorption, while vitamin K performs the carboxylation that lets those proteins bind calcium. Neither step substitutes for the other.
Both phylloquinone and the menaquinones need bile salts and dietary fat for micellar uptake, so an oil carrier raises the absorbed fraction against a fasted dose. Vitamin K softgels are formulated in an oil base for this reason.
Phylloquinone and the menaquinones are lipophilic and are absorbed only after incorporation into mixed micelles, which requires bile salts and pancreatic lipase. When bile flow is low, fat-soluble vitamin uptake drops with it. Supplemental bile components are used in formulation for exactly this step, and the relationship is standard digestive physiology rather than a trial finding.
Vitamin K arrives in food dissolved in fat, and lipase must hydrolyse that fat before the vitamin can partition into a micelle. This is why vitamin K taken with a meal containing fat is absorbed more completely than on an empty stomach. The step is textbook digestion and applies to all four fat-soluble vitamins.
Blended enzyme products supply lipase alongside protease and amylase, and it is the lipase fraction that matters for vitamin K. The support is indirect: the enzymes act on the meal, not on the vitamin. Where fat digestion is already adequate, adding enzymes has no further absorption step to contribute.
Krill oil carries its fatty acids largely as phospholipids, which emulsify readily and form micelles without much bile input. Dissolving vitamin K in that matrix presents it to the intestine already dispersed. This is a delivery relationship, so it changes how much is absorbed rather than what the vitamin does once inside.
Lecithin phospholipids lower interfacial tension and help lipophilic actives disperse in aqueous gut contents. Vitamin K softgels commonly use a lecithin or oil base for this reason. The mechanism is physical dispersion. No chemical change to the vitamin occurs.
Phosphatidylcholine forms the mixed micelles that ferry fat-soluble vitamins to the enterocyte brush border. It is used both as an isolated excipient and as the active fraction of lecithin. As with any vehicle, it affects delivery and not the carboxylation chemistry downstream.
Menaquinone-7 and nattokinase are both products of Bacillus subtilis natto fermentation and often co-occur in a finished formula. Vitamin K supports the carboxylation of clotting factors, while nattokinase has fibrinolytic activity, so the two touch haemostasis from opposite ends. There is no combination trial establishing a net direction, and the honest description is that they are co-sourced rather than complementary.
Large alpha-tocopherol intakes have been documented to lower measures of vitamin K-dependent carboxylation, through competition for shared lipid transport and through tocopherol quinone metabolites that interfere with the vitamin K cycle. The interaction shows at supplemental amounts, not at food intakes. Where both are formulated together, the amounts and the timing matter.
Tocotrienols and the menaquinones both carry unsaturated isoprenoid side chains and travel in the same lipoprotein fractions after absorption. Competition for micellar space and for lipoprotein carriage is plausible on that basis. It is a mechanistic expectation from shared chemistry, not something measured in a human trial that has been located.
Retinol and vitamin K both need bile salt micelles to reach the enterocyte, and at high single doses the fat-soluble vitamins compete for that finite micellar capacity. In a mixed formula at ordinary amounts the competition is small. It becomes worth spacing doses only when one of them is supplied in a large isolated amount.
Beta-carotene is one of the most micelle-hungry dietary lipophiles and reduces the uptake of other fat-soluble compounds taken at the same time. Vitamin K sits in the same queue. This is an absorption interaction only. Neither affects the other's function once in circulation.
Colonic bacteria produce menaquinones ranging from MK-6 to MK-11, and some Lactobacillus and Bacillus species are documented menaquinone producers. How much of that bacterial pool is absorbed from the colon remains uncertain, since absorption there lacks bile. The relationship supports the body's own menaquinone supply and should be read as contributory, not as a substitute for dietary intake.
Bifidobacteria are part of the community whose metabolism shapes the colonic menaquinone pool, though the highest producers are Bacteroides and Escherichia species. Colonic absorption of these long-chain forms is limited and poorly quantified. The connection is real microbiology stated at its true confidence, not a claim that a probiotic supplies vitamin K.
The vitamin K cycle depends on reduction of the quinone to the hydroquinone form, work done by NAD(P)H-dependent reductases whose flavin cofactors derive from riboflavin. Riboflavin status therefore sits upstream of the reducing environment the vitamin K cycle needs. The link is biochemical and indirect. No clinical measurement of the pairing has been located.
Vitamin K carboxylates osteocalcin, the bone protein that binds calcium into the mineral matrix, while boron influences the handling of calcium and magnesium in bone. Both are supporting inputs to normal bone maintenance through different steps. The pairing rests on separate mechanisms rather than a tested combination.
Strontium is taken up into hydroxyapatite in place of some calcium, and carboxylated osteocalcin is the protein that binds calcium ions during that mineralisation. Because strontium alters the mineral phase itself, describing the pair as simply additive would overstate what is known. It is a modulating relationship at early confidence.
Nothing specific on file for Vitamin K. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Vitamin K actually does.
Vitamin K is the required helper for the enzyme that adds a carboxyl group to certain glutamate spots on proteins. That change is what gives those proteins their calcium-binding sites.
3 more mechanisms
Each carboxylation uses up the active form of vitamin K and leaves a spent one, which two enzymes flip straight back. That recycling loop is why a small pool of vitamin K supports a lot of work.
Osteocalcin, made by bone-building cells, has to go through that vitamin K carboxylation step before it can bind calcium in the bone matrix. The uncarboxylated version in blood is used as a marker of vitamin K status.
Matrix Gla protein is made in blood vessel muscle and cartilage and needs the same carboxylation before it can bind calcium. It is one of the vitamin K-dependent proteins involved in normal calcium handling in soft tissue.
Where Vitamin K comes from.
The K2 in most supplements is made by bacteria, the same ones behind the Japanese food natto, and then cleaned up and put into an oil or a capsule. K1 and MK-4 are usually built in a lab instead. Both routes give a defined molecule. They just get there differently.
What this route gives you
The same molecule is reached more than one way. Which route a given product used is a manufacturing choice, and the finished compound is the same either way.
6 steps on record
For menaquinone-7, a defined natto strain is grown on a cooked legume substrate. The bacterium produces MK-7 as part of its own electron transport chain, so the vitamin is a metabolite of the culture rather than something added to it.
Temperature, aeration and culture time govern how much MK-7 accumulates and in what cis to trans ratio. The all-trans geometry is the biologically active one, and process control is what determines it.
The lipophilic menaquinone is taken into an organic solvent or an oil phase and separated from the spent biomass.
Column separation removes fermentation by-products and cis isomers. Assays report all-trans content, which is why two products at the same stated amount can differ in active geometry.
Phylloquinone and menaquinone-4 are usually made synthetically: a naphthoquinone core is coupled to a phytyl or geranylgeranyl side chain, then isomer-purified. This is a different route from fermentation and yields the same defined molecule.
MK-7 is unstable next to some mineral salts, particularly at high pH, so it is often microencapsulated or suspended in an oil such as MCT before being put into a softgel, tablet or powder blend.
Getting Vitamin K from food.
The whole-food sources on file. A supplement closes the gap, it does not replace dinner.
A gram-for-gram figure (how much of each you would eat to match a dose) will appear here once it is sourced and reviewed. This page will not print a number it cannot cite.
The forms it comes in.
9 more forms
The essence, in one line each.
- Pooling 16 randomized trials in 6,425 postmenopausal women studied for a diagnosed bone condition, vitamin K2 supplementation improved lumbar spine bone mineral density and lowered undercarboxylated osteocalcin.Meta-analysis, in postmenopausal women with osteoporosis. Ma et al., 2022 (Frontiers in Public Health). PMID 36033779 ↗
8 more findings
- In 244 healthy postmenopausal women, three years of 180 mcg per day menaquinone-7 reduced carotid-femoral pulse wave velocity, a marker of arterial stiffness, and cut inactive matrix Gla-protein by about 50 percent versus placebo.Randomised trial. Knapen et al., 2015 (Thrombosis and Haemostasis). PMID 25694037 ↗
- Across trials in middle-aged and older adults, vitamin K supplementation raised the active carboxylated form of the bone protein osteocalcin and lowered its inactive form, reflecting greater osteocalcin activation.Systematic review. Xie et al., 2024 (Bone & Joint Research). PMID 39657786 ↗
- In a meta-analysis of randomized trials, vitamin K supplementation did not have a detectable effect on body measurements, inflammation, or blood lipids, but it did reduce a measure of insulin resistance.Meta-analysis. Zhao et al., 2024 (Journal of nutritional science). PMID 38282652 ↗
- The Cochrane reviewers found the available trial evidence too limited to draw firm conclusions about vitamin K supplementation in this group, which is a shortage of data and not a finding of no effect.Systematic review. Jagannath et al., 2020 (Cochrane Database of Systematic Reviews). PMID 32497260 ↗
- A systematic review of parental refusal of newborn vitamin K administration and its association with refusal of other preventive measures. This is an association in survey and record data, not a causal finding.Systematic review. Khan et al., 2022 (JPMA: The Journal of the Pakistan Medical Association). PMID 37013297 ↗
- In a rat model, vitamin K supplementation was examined against testicular testosterone production. The finding is preclinical and does not transfer to people.Animal study. Murakami et al., 2026 (Foods). PMID 41897792 ↗
- Phylloquinone. Phylloquinone is the plant form and the reference form of vitamin K in human status work. In a 3-year double-blind randomised trial, 452 men and women aged 60 to 80, all calcium and vitamin D replete, received a multivitamin containing either 500 micrograms per day of phylloquinone or none, plus calcium 600 mg and vitamin D 400 IU. The supplemented group showed significantly higher plasma phylloquinone and significantly lower percentage undercarboxylated osteocalcin, but no differences in femoral neck, lumbar spine or total-body bone mineral density at any measured site (n = 401 completers, intent to treat). A separate 2 to 4 year double-blind placebo-controlled trial in 440 postmenopausal women with osteopenia, using 5 mg per day, reported the same result on bone mineral density. Clinical fractures were fewer in the phylloquinone arm (9 versus 20, p = 0.04) and the authors state the study was not powered to examine fractures, concluding that 5 mg for 2 to 4 years does not protect against age-related decline in bone mineral density but may protect against fractures. Pharmacologically, in two randomised trials in 144 patients on phenprocoumon, 5 mg of oral phylloquinone lowered the International Normalised Ratio measured at 24 and 48 hours, with tablets at least as clinically effective as an oral solution in countering vitamin K antagonists, which is the basis for phylloquinone being the form used in that clinical setting.Clinical trial. Booth 2008, phylloquinone 500 mcg/d for 3 years, bone loss in elderly men and women. doi 10.1210/jc.2007-2490 ↗
- Menaquinone-4. Nearly all randomised bone research on MK-4 sits at the Japanese pharmacological dose of 45 mg per day rather than at supplement-scale microgram doses. A 2019 systematic review and meta-analysis of 18 randomised controlled trials covering 8,882 patients found menatetrenone improved lumbar bone mineral density against placebo (5 studies, n = 658, mean difference 0.05 g/cm2, 95% CI 0.01 to 0.09) and decreased the ratio of undercarboxylated osteocalcin to osteocalcin (2 studies, n = 75, mean difference minus 21.78 percent, 95% CI minus 33.68 to minus 9.87), while the reduction in vertebral fracture risk was not statistically significant (5 studies, n = 5,508, risk ratio 0.87, 95% CI 0.64 to 1.20). Adverse events were more frequent than on placebo (risk ratio 1.47, 95% CI 1.07 to 2.02) with no significant difference in serious adverse events, and the authors state the benefit in fracture risk control is uncertain. In a multicentre double-blind trial in 236 Chinese postmenopausal women comparing 45 mg per day with alfacalcidol for 1 year, with no placebo arm, lumbar spine and trochanter bone mineral density rose from baseline by 1.2 and 2.7 percent. At nutritional doses the picture is different: in a randomised comparison in healthy Japanese women, a single 420 microgram dose and 60 micrograms per day for 7 days left MK-4 undetectable in the serum of all subjects at every timepoint.Clinical trial. Su 2019, efficacy and safety of menatetrenone in osteoporosis, 18 RCTs, 8,882 patients. doi 10.1007/s00198-019-04853-7 ↗
Chosen from the 183 we read for Vitamin K.
The studies, linked.
12 sources behind our Vitamin K verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Meta-analysisEfficacy and safety of non-vitamin K antagonist oral anticoagulants vs. warfarin in Japanese patients with atrial fibrillation – meta-analysis.PubMed ↗Circulation journal : official journal of the Japanese Circulation Society, 2015, cited 34 times, open access
11 more linked trials
- Meta-analysisNon-vitamin K antagonist oral anticoagulants in the cardioversion of patients with atrial fibrillation: systematic review and meta-analysisPubMed ↗Clinical Research in Cardiology, 2015, cited 29 times
- ReviewNew oral anticoagulants: their advantages and disadvantages compared with vitamin K antagonists in the prevention and treatment of patients with thromboembolic eventsPubMed ↗Therapeutics and Clinical Risk Management, 2015, cited 377 times, open access
- ReviewNon-vitamin K antagonist oral anticoagulants (NOACs) for stroke prevention in Asian patients with atrial fibrillation: time for a reappraisal.PubMed ↗International journal of cardiology, 2015, cited 160 times, open access
- ReviewNon‐vitamin K antagonist oral anticoagulants (NOACs) in patients with concomitant atrial fibrillation and heart failure: a systemic review and meta‐analysis of randomized trialsPubMed ↗European Journal of Heart Failure, 2015, cited 123 times, open access
- PubMed ↗
- ReviewRenal function and non-vitamin K oral anticoagulants in comparison with warfarin on safety and efficacy outcomes in atrial fibrillation patients: a systemic review and meta-regression analysisPubMed ↗Clinical Research in Cardiology, 2015, cited 93 times
- ReviewPrevention of vasculopathy by vitamin K supplementation: can we turn fiction into fact?PubMed ↗Atherosclerosis, 2015, cited 61 times
- ReviewProthrombin complex concentrate for reversal of vitamin K antagonist treatment in bleeding and non-bleeding patients.PubMed ↗The Cochrane database of systematic reviews, 2015, cited 57 times, open access
- Clinical trialReal-world Comparative Effectiveness of Dabigatran Versus VKAClinicalTrials.gov ↗56,039 participants, Completed
- Clinical trialAn Observational Cohort Study of the Risk of Thromboembolic Events Among Adult Patients Treated With KCENTRA® Compared With Plasma for Urgent Reversal of Vitamin K Antagonist Therapy in the Setting of Acute Major BleedingClinicalTrials.gov ↗2,238 participants, Completed
- Clinical trialA Prospective Observational Study Assessing the Management of Anticoagulation With Vitamin K Antagonists in Patients With Nonvalvular Atrial Fibrillation Treated in Cardiology PracticesClinicalTrials.gov ↗1,013 participants, Completed
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 13,819 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Vitamin K is, not how risky it is. A report is not proof Vitamin K caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.