Cannabinoids.
Research-backed compound with potential health benefits. Interacts with your body's endocannabinoid system. Helps manage anxiety, can improve sleep, and might reduce some types of pain. Think of it as a system regulator.
Reviewed March 2026
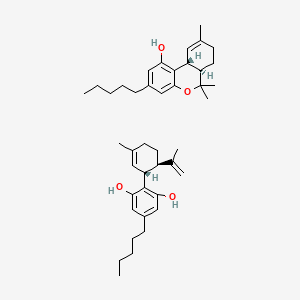 Compound
- Category
- Compound
What Cannabinoids is, and what it does.
- Does it work
- Maybe. For specific issues like anxiety, the evidence is decent. For the million other claims, it's weaker. The market is a minefield of bad products.
- How much to take
- Highly individual. Start low, 10-20mg per day. Slowly increase every few days until you find what works for you. There's no standard dose.
- Time to feel it
- An oil taken with food peaks in the blood within a couple of hours. Day-to-day steadiness is something people describe after two to four weeks of consistent use.
- The first dose
- Probably nothing. Some might feel a subtle calm within an hour or two, but for most, effects build over several days of consistent use.
- With regular use
- After a few weeks, a sustained reduction in baseline anxiety is the main goal. Sleep patterns may become more regular. It's about gradual effects, not a quick change.
- How well tolerated
- Usually well tolerated, with tiredness and a dry mouth the common reports. They compete for the same liver enzymes as many medicines, so check with your doctor if you take any.
- How it feels
- A gentle easing of tension, not sedation. The edge is taken off. You feel more like yourself on a good day, not like you've taken something.
- The overlooked benefit
- They park in body fat and leave slowly, so blood levels keep climbing over the first week or two of daily use. Consistent timing tells you more than any single serving does.
10 to 25mg a day is where Cannabinoids works.
Source: Based on CBD/hemp extract dosing; full-spectrum product research
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
Cannabinoids is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.
- sleep quality ratings with evening dosingRandomised trial
- self-rated calm under acute stressRandomised trial
4 more claims
- higher oral absorption alongside a fat-containing mealRandomised trial
- interaction potential with medicines cleared by CYP3A4, CYP2C9 and CYP2C19Narrative review
- CB1 and CB2 receptor signalling in nerve and immune tissueIn vitro study
- accumulation in adipose tissue and a long elimination phaseNarrative review
Questions people ask about Cannabinoids.
- Will this get me high?
- No. CBD is non-psychoactive. THC is the compound that gets you high. Reputable products have less than 0.3% THC.
5 more questions
- Is it legal?
- Hemp-derived CBD with less than 0.3% THC is federally legal in the US, but some state laws vary. Check your local rules.
- What's the difference between full-spectrum, broad-spectrum, and isolate?
- Full-spectrum has all plant compounds, including a tiny bit of THC. Broad-spectrum has everything but the THC. Isolate is just pure CBD. Many believe full-spectrum works best.
- Can I take it every day?
- Yes, most research shows consistent daily use is most effective. It's not considered addictive.
- How long until it works?
- For oils, 30-90 minutes. For gummies, 1-2 hours. But the real benefits for anxiety build over days or weeks.
- Will I fail a drug test?
- It's possible with full-spectrum products. The tiny amount of THC can build up and trigger a positive test. If you're tested, use a broad-spectrum or isolate product to be safe.
Why these belong in the same formula, 11 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
Cannabinoids are strongly lipophilic and dissolve poorly in water, so they are almost always carried in a fat. Medium-chain triglycerides act as that carrier and keep the compound in solution through the gut lumen, where mixed micelle formation governs uptake. Taking a cannabinoid preparation with dietary fat raises systemic exposure compared with a fasted dose. This is a formulation and absorption relationship, not an added biological effect.
Phospholipids from lecithin lower interfacial tension and let an oily cannabinoid extract disperse as fine droplets in aqueous gut contents. Smaller droplets present more surface area to bile salts and pancreatic lipase. Emulsified and self-emulsifying preparations are a common answer to the variability seen with plain oil solutions. The pairing is formulation convention rather than a biological interaction.
Phosphatidylcholine is used to build liposomal and phospholipid-complexed cannabinoid preparations. The phospholipid bilayer holds the lipophilic molecule and travels with the normal lipid absorption route. Formulators use it for the same reason they use lecithin, to make an oil-soluble compound behave predictably in water.
Piperine inhibits several CYP enzymes and UDP-glucuronosyltransferases that also handle cannabinoid clearance. Combining the two can raise cannabinoid blood levels above what the same dose would otherwise give. The direction is predictable from the enzymology, but the size of the shift in people has not been characterised for this specific pair. Read it as a reason to be deliberate about dosing rather than as a benefit.
Quercetin inhibits CYP3A4 and CYP2C9 in laboratory systems, and those are among the enzymes that oxidise cannabinoids in the liver. Co-exposure would be expected to slow clearance. The evidence is enzymatic rather than clinical, so this belongs in the flag column rather than the benefit column.
The body's own cannabinoid-receptor ligands are built from long-chain polyunsaturated fatty acids, and dietary fatty acid supply changes the pool available for that synthesis. EPA and DHA also form their own ethanolamide derivatives that interact with the same receptor family. Plant cannabinoids act on that system from the outside, so the two arrive at the same receptors by different routes. This is mechanistic reasoning, not a tested combination.
Melatonin and cannabinoids appear together in evening formulations because both are used around sleep timing. Their mechanisms are separate, melatonin acting at MT1 and MT2 receptors and cannabinoids at CB1, so the overlap is in the felt effect rather than the pathway. Sedation can stack, which matters for anyone driving or operating machinery.
Valerian constituents act on GABAergic signalling and cannabinoids modulate neurotransmitter release presynaptically, so drowsiness from the two can add up. No trial has measured the pair. The practical point is additive sedation, and it is worth naming rather than assuming.
Honokiol and magnolol act as positive modulators at GABA-A receptors, a separate site from the cannabinoid receptors. Both are used in calm and sleep formulations, so their subjective effects can compound. Nothing has been measured in combination.
Cannabinoid oils oxidise and degrade with light, heat and air, and tocopherols are the usual chain-breaking antioxidant added to slow that. The vitamin protects the carrier oil and the cannabinoid content of the finished product. This is shelf stability, not a physiological synergy.
Caffeine blocks adenosine receptors while cannabinoids act presynaptically at CB1 to change neurotransmitter release, and adenosine and cannabinoid signalling converge on some of the same striatal circuits. Products pair them for a stimulant plus calm effect. The interaction is described mechanistically in animal work rather than measured in people.
Nothing specific on file for Cannabinoids. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Cannabinoids actually does.
Cannabinoids act on two receptor types that are part of the body's own signaling system, affecting nerve signal release and immune cell activity.
3 more mechanisms
Cannabinoids dissolve poorly in water and are absorbed mainly through fat-related pathways in the gut, which is why taking them with a fatty meal increases how much gets into the blood.
Cannabinoids taken by mouth get heavily processed by liver enzymes before reaching circulation, which is a big reason blood levels vary so much between people taking the same dose.
The body's own cannabinoid-like signaling molecules are made on demand rather than stored, and specific enzymes break them down after use.
Where Cannabinoids comes from.
They come from the hemp plant. The plant is dried, the oily fraction is pulled out with pressurised carbon dioxide or cold alcohol, then cleaned up and either left as a whole-plant oil, stripped of THC, or purified all the way down to a single white powder.
What this route gives you
Made from a plant. What ends up in the capsule tracks the harvest, so batch testing and a stated marker matter more here than with a made molecule.
6 steps on record
Flower and leaf material from Cannabis sativa cultivars bred for low THC, harvested, dried and milled
Controlled heating converts the acidic cannabinoids in the raw plant, CBDA and THCA, to their neutral forms before or during extraction
CO2 extraction runs at high pressure and leaves no solvent residue to remove. Cold ethanol extraction is faster and higher-yielding but co-extracts more chlorophyll and waxes and requires solvent recovery
The crude extract is dissolved in cold ethanol so waxes and lipids precipitate out, then filtered and the solvent stripped
Distillation concentrates the cannabinoid fraction. Chromatography is the step that removes THC to make a broad-spectrum material or isolates a single cannabinoid to crystalline purity
The purified material is dissolved in a food oil, emulsified for aqueous formats, or crystallised and dried as an isolate powder
The forms it comes in.
3 more forms
The essence, in one line each.
- This meta-analysis of 13 trials found inconsistent and often trivial effects of cannabidiol (CBD) on circulating inflammatory markers, with no statistically significant changes in the pooled results for IL-6, IL-8, IL-10, or TNF-α.Meta-analysis. Candeloro et al., 2025 (International journal of molecular sciences). PMID 41373770 ↗
4 more findings
- A broad spectrum cannabidiol supplement did not produce a detectable difference in 10 minute cycle ergometer performance compared with placebo in healthy adults.Randomised trial. Gillham et al., 2024 (European journal of sport science). PMID 38956805 ↗
- Daily use of a broad spectrum cannabidiol supplement produced measurable cannabinoid concentrations in urine, which matters for athletes subject to testing.Randomised trial. Gillham et al., 2026 (Medicine and science in sports and exercise). PMID 40920736 ↗
- In a meta-analysis of studies in people with a diagnosed wasting syndrome, cannabinoids did not show a significant benefit for appetite or weight gain.Meta-analysis, in people with cancer-associated cachexia. Simon L et al., 2022 (Journal of Cachexia, Sarcopenia and Muscle). PMID 34881518 ↗
- Cannabinoids are named among the dietary bioactives appraised, with the authors describing the human trial base for cognitive outcomes in older adults as small and preliminary.Narrative review. Kumari A et al., 2026 (Nutrients). PMID 41901082 ↗
Chosen from the 1,822 we read for Cannabinoids.
The studies, linked.
1 source behind our Cannabinoids verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Clinical trialA Single-centre, Pilot, Randomized Controlled Trial of Oral Cannabinoids for Improving Pain Disability in Patients With Chronic PainClinicalTrials.gov ↗51 participants, Completed
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 289 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Cannabinoids is, not how risky it is. A report is not proof Cannabinoids caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.