Ingredients/Compound/Levomefolate

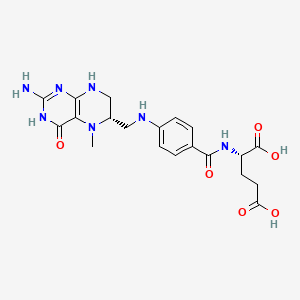
Levomefolate.

Read pending.Levomefolate is in the library. The clinical read is in the queue.

Research-backed compound with potential health benefits. Delivers the usable form of Vitamin B9 (folate) directly to your body. It bypasses potential conversion issues (like the MTHFR gene), supporting mood, brain function, and healthy cell growth.

400 to 800mcgDaily amount

Reviewed July 2026

Compound
LevomefolateIngredientMD
Category
Compound

What Levomefolate is, and what it does.

Does it work
Yes. A non-negotiable for many with the MTHFR variant or for those whose antidepressants aren't fully working. It's a key piece of the puzzle.
How much to take
For general support, 400-1000 mcg daily. For mood, clinical studies use 7.5mg to 15mg (7,500-15,000 mcg), but that's doctor territory. Don't start there.
Time to feel it
A median of about 36 weeks of daily intake.
The first dose
Nothing. Your body needs weeks to build up levels and put it to work. Be patient with this one.
With regular use
A more stable mood, sharper thinking, and healthier homocysteine levels. For pregnancy, it's a critical player in healthy fetal development.
How well tolerated
Well tolerated. The main heads-up is that it can mask a B12 deficiency. If you're taking high doses long-term, get your B12 checked periodically.
How it feels
Subtle. You won't 'feel' it kick in. It's more about the absence of negatives—less brain fog, a more even keel—that you notice after a month or two.
The overlooked benefit
It fills the folate pool even when B12 is low, which can mask a low B12 reading on a blood test. That's the reason it's usually paired with B12 rather than taken alone.

How common this is.

Public health figures for this ingredient, reported by the agencies that publish them, cited and dated.

United States

Women of reproductive ageNHANES 2011 to 2016

About 19% of US women of reproductive age

have blood folate below the level associated with the lowest risk of neural tube defects.

Pfeiffer et al. (CDC), American Journal of Clinical Nutrition 2019, NHANES 2011 to 2016, RBC folate insufficiency 18.6% in women aged 12 to 49. ↗
4 more figures for United States
Women aged 71 and over, WWEIA NHANES 2013 to 2016

About 27% of US women aged 71 and over

take in less folate from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 22 (folate as dietary folate equivalents), females 71+: 27% below EAR (SE 2.7). ↗
Women aged 19 to 50, WWEIA NHANES 2013 to 2016

About 18% of US women aged 19 to 50

take in less folate from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 22 (folate as dietary folate equivalents), females 19-50: 18% below EAR (SE 1.7). ↗
Girls aged 14 to 18, WWEIA NHANES 2013 to 2016

About 21% of US girls aged 14 to 18

take in less folate from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 22 (folate as dietary folate equivalents), females 14-18: 21% below EAR (SE 4.3). ↗
Men aged 19 and over, WWEIA NHANES 2013 to 2016

About 8% of US men aged 19 and over

take in less folate from food and drink than the estimated average requirement.

USDA ARS, Usual Nutrient Intake from Food and Beverages, by Gender and Age, WWEIA NHANES 2013-2016, Table A 22 (folate as dietary folate equivalents), males 19+: 8% below EAR (SE 0.9). ↗

United Kingdom

Women aged 75 and overNDNS 2014/15 to 2015/16

About 8% of UK women aged 75 and over

take in less folate from food than the lower reference nutrient intake (LRNI).

National Diet and Nutrition Survey: Results from Years 7 and 8 (combined) of the Rolling Programme (2014/15 to 2015/16), Table F 'Average daily intake as a percentage of the RNI... and proportion with intakes below the LRNI', Folate row, p.18 ↗Fieldwork 2014/15 to 2015/16 (NDNS Rolling Programme Years 7 and 8 combined)
4 more figures for United Kingdom
Women, NDNS 2016 to 2019

About 89% of UK women of childbearing age

have blood folate below the level associated with the lowest risk of neural tube defects.

NDNS Years 9 to 11 of the Rolling Programme (2016/17 to 2018/19), statistical summary, section 4.3 Folate ↗

Canada

WomenCHMS 2007 to 2009

About 22% of Canadian women of childbearing age

have red blood cell folate concentrations below the level associated with the lowest risk of neural tube defects.

Colapinto, O'Connor, Tremblay, CMAJ 2011;183(2):E100, "Folate status of the population in the Canadian Health Measures Survey" ↗
3 more figures for Canada
Women aged 71 and over, CCHS 2015

About 60% of Canadian women aged 71 and over

take in less folate from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Folate (mcg/d (DFE)), Female, 71 years and over ↗
Girls aged 14 to 18, CCHS 2015

About 38% of Canadian girls aged 14 to 18

take in less folate from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Folate (mcg/d (DFE)), Female, 14-18 years ↗
Men aged 19 and over, CCHS 2015

About 15% of Canadian men aged 19 and over

take in less folate from food than the estimated average requirement.

Health Canada/Statistics Canada, Total Usual Intakes from Food (2015 CCHS, Nutrition), Open Government Portal dataset; Folate (mcg/d (DFE)), Male, 19 years and over ↗

Australia

Men aged 18 and overNNPAS 2023 to 2024

About 6% of Australian men aged 18 and over

take in less folate from food and drink than the estimated average requirement.

ABS, Usual nutrient intakes, 2023, Folate (vitamin B9) section ↗
2 more figures for Australia
Women aged 75 and over, NNPAS 2023

About 7.6% of Australian women aged 75 and over

take in less folate from food and drink than the estimated average requirement.

ABS, National Nutrition and Physical Activity Survey 2023, Usual nutrient intakes data cube (UNIDC05.xlsx), Table 5.17 Usual intake of dietary folate equivalents, by age and sex, Females with usual intake less than EAR (%) ↗
Girls aged 12 to 17, NNPAS 2023

About 6.5% of Australian girls aged 12 to 17

take in less folate from food and drink than the estimated average requirement.

ABS, National Nutrition and Physical Activity Survey 2023, Usual nutrient intakes data cube (UNIDC05.xlsx), Table 5.17 Usual intake of dietary folate equivalents, by age and sex, Females with usual intake less than EAR (%) ↗

Population figures from public health data. Context for the category, not a statement about any individual and not a claim about this product.

400 to 800mcg a day is where Levomefolate works.

How much to take a dayHigh confidence
400 to 800mcg
Daily maintenanceThe everyday amount, and where most daily supplements sit. This is the one you take month after month.
1,000mcgClinical territory. Trials run high on purpose, for a set number of weeks, against one measured outcome. Impressive to hit, and not what a daily product is for.
Above 1,000mcgPast what the research covers. More capsules rather than more effect.
MORE EFFECT ↑0800mcg1,000mcg plateauDAILY DOSE →
The shaded band is where the dosing trials landed.

Source: NIH ODS + Bailey 2015 review

How long it takesStrong
WHAT THE TRIALS MEASUREDthe level the trials measuredDay 0TIME ON IT →
Builds over a median of about 36 weeks of daily intake
What the trial measured, in its words

A systematic review and Bayesian meta-analysis drew on 108 articles from 14,002 screened records and modelled blood folate against folic acid intake using one-compartment pharmacokinetic models. Red blood cell folate rose 1.78 fold from baseline to steady state at 375 to 570 ug folic acid per day, and reaching that steady state took a median of 36 weeks, 95% credible interval 27 to 52 weeks. Serum or plasma folate rose 11.6% for every 100 ug per day of folic acid intake, 95% credible interval 8.4 to 14.9.

The proof, claim by claim.

What these words mean

These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.

Read pending.

Levomefolate is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.

  • Plasma and red cell folate statusRandomised trial
  • Homocysteine already in the normal rangeMeta-analysis
3 more claims
  • Folate status in people carrying reduced-activity MTHFR variantsRandomised trial
  • Folate status before and during pregnancyRandomised trial
  • Mood steadiness alongside standard careRandomised trial

Questions people ask about Levomefolate.

Is this better than folic acid?
For many, yes. If you have an MTHFR gene variation, your body struggles to convert folic acid. This is the finished, usable product.
3 more questions
What's MTHFR?
A common gene variation that slows down the conversion of folic acid into its active form. Up to 40% of people have it.
Any side effects?
Rare at standard doses. Very high doses can sometimes cause jitteriness, irritability, or trouble sleeping. Start low.
Can I just get this from food?
You get folate from leafy greens and legumes, which is great. But getting the high therapeutic doses used for mood support from food alone is nearly impossible.
Pairs well with23 on file
Levomefolate + Vitamin B12 (Cobalamin)one-carbon cycle cofactor pair
Levomefolate + RiboflavinFAD cofactor for MTHFR
Levomefolate + P5P (Pyridoxal-5-Phosphate)shared homocysteine handling
Levomefolate + Cholineinterchangeable methyl pools
Why these belong in the same formula, 23 pairings

Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.

Levomefolate + Vitamin B12 (Cobalamin)one-carbon cycle cofactor pair

Methionine synthase hands the methyl group from 5-methyltetrahydrofolate to cobalamin and then to homocysteine. Without enough B12 the folate pool stays stuck in its methyl form and cannot re-enter the cycle.

Methylcobalamin is the cofactor form that accepts the methyl group carried by levomefolate. Pairing the two active forms keeps the remethylation step supplied on both sides.

Levomefolate + RiboflavinFAD cofactor for MTHFR

MTHFR, the enzyme that makes 5-methyltetrahydrofolate, carries an FAD cofactor derived from riboflavin. Riboflavin status shapes how much active folate the body can generate itself.

Levomefolate + P5P (Pyridoxal-5-Phosphate)shared homocysteine handling

Levomefolate feeds the remethylation route while pyridoxal-5-phosphate runs the transsulfuration route through cystathionine beta-synthase. The two routes divide the same homocysteine pool between them.

Betaine remethylates homocysteine through BHMT without using folate. It covers the same step when folate-dependent remethylation is running slowly.

Levomefolate + Cholineinterchangeable methyl pools

Choline is oxidised to betaine and becomes a methyl donor, so choline and folate intake substitute for each other. Low intake of one raises demand on the other.

Levomefolate + L-Serineone-carbon donor

Serine hydroxymethyltransferase moves a one-carbon unit from serine onto tetrahydrofolate, which is where most of the folate-borne methyl groups originate. Serine supply sets the loading rate of the folate pool.

Levomefolate + Glycineglycine cleavage one-carbon input

The glycine cleavage system transfers a carbon unit to tetrahydrofolate, a second entry point into the same pool. Glycine and serine interconvert, so both sit upstream of methylfolate.

Levomefolate + SAM-e (S-Adenosyl Methionine)downstream product and feedback

Methyl groups delivered by levomefolate end up in methionine and then SAM-e, the universal methyl donor. SAM-e also feeds back on MTHFR, so the two sit at opposite ends of one loop.

Folinic acid enters the folate pool upstream of the MTHFR step and can be converted onward, while levomefolate enters at the methyl end. Together they cover both sides of the folate cycle.

Levomefolate + Zinccofactor for folate handling enzymes

Intestinal folate conjugase and methionine synthase reductase depend on zinc. Low zinc status slows how dietary polyglutamate folate is released and how the methylation cycle is maintained.

Levomefolate + Folic acidEstablished shared transport and reduction biochemistry

Folic acid and levomefolate cross the intestinal wall through the same proton-coupled folate transporter and reduced folate carrier, so they compete for the same route when given together. Folic acid additionally requires two reduction steps by dihydrofolate reductase before it becomes usable, while levomefolate is already at the circulating oxidation state. High folic acid intake also raises unmetabolised folic acid in plasma, a marker rather than an outcome. Combining both in one formula makes the delivered folate picture harder to read.

Levomefolate + Vitamin CEstablished folate chemistry

Reduced folates including 5-methyltetrahydrofolate oxidise readily in air and in solution, which is the main stability problem in formulating them. Ascorbate is the conventional antioxidant used to protect reduced folate in liquids and in the gut lumen. The role is chemical protection, not a change in transport or metabolism. This is settled formulation chemistry.

Levomefolate + IronEstablished erythropoiesis biochemistry and long-standing co-formulation

Red blood cell production needs both folate for DNA synthesis in dividing precursors and iron for haemoglobin, which is why the two are combined in prenatal and blood-support formulas. They act at different steps and neither substitutes for the other. Iron salts are oxidising and can degrade reduced folate in a shared matrix, so formulators separate or protect them. Read the pairing as complementary roles in one process.

Levomefolate + L-methionineEstablished one-carbon metabolism

Methionine synthase transfers the methyl group from 5-methyltetrahydrofolate to homocysteine to regenerate methionine, which is then activated to S-adenosylmethionine. Supplying methionine loads the same cycle from the product end rather than the donor end. High methionine intake without adequate folate, B12 and B6 raises circulating homocysteine, a marker. The two sit on opposite sides of one reaction, which is why they are discussed together.

Levomefolate + NACEstablished transsulfuration biochemistry

Homocysteine has two fates: remethylation to methionine, which 5-methyltetrahydrofolate drives, and transsulfuration to cysteine and onward to glutathione. NAC supplies cysteine directly and reduces the pull on the transsulfuration branch. The two therefore address the same intermediate from different directions. Homocysteine is a biochemical marker, not an outcome in itself.

Levomefolate + InositolEstablished co-supplementation practice in reproductive-support formulas

Myo-inositol is combined with active folate in preconception and reproductive-support products, where each has its own established role. Inositol works in phosphoinositide signalling and insulin signal transduction, unrelated to one-carbon transfer. The pairing stacks two independent inputs in one formula. It is category practice rather than a demonstrated interaction.

Levomefolate + Vitamin B3 (niacin)Established NADPH-dependent folate biochemistry

Methylenetetrahydrofolate reductase, the enzyme that produces 5-methyltetrahydrofolate in the body, uses NADPH as its reducing cofactor, and NADPH derives from niacin-based nucleotides. Dihydrofolate reductase is NADPH-dependent too. Supplying the finished 5-MTHF bypasses the MTHFR step, so the dependency matters more for the endogenous route than for the supplemented one. This is textbook cofactor biochemistry.

Levomefolate + Green tea extract (EGCG)Established in vitro enzyme inhibition

EGCG inhibits dihydrofolate reductase in cell-free and cell-culture systems, which is the step that converts folic acid toward usable reduced folate. Levomefolate does not need that step, so the interaction is more relevant to folic acid than to the active form. The finding is in vitro and its size in people at dietary catechin intakes is not established. Read it as mechanistic.

Levomefolate + MagnesiumEstablished cofactor chemistry in methylation reactions

Magnesium is a required cofactor for the ATP-dependent activation of methionine to S-adenosylmethionine and for many downstream methyltransferases. That places it in the same cycle that 5-methyltetrahydrofolate feeds. Deficiency of magnesium is not the usual bottleneck in that cycle, so the relationship is supportive rather than rate-setting. This is standard biochemistry.

Levomefolate + CalciumEstablished salt chemistry of the commercial ingredient

The most widely used commercial form of levomefolate is its calcium salt, so calcium is present as the counterion by design rather than as an added partner. The salt improves crystallinity and handling of an otherwise unstable reduced folate. Calcium from other sources in the same formula does not add to that role. The relationship is formulation chemistry.

Levomefolate + L-cysteineEstablished transsulfuration biochemistry

Cysteine is the product of the transsulfuration branch that consumes homocysteine, the same intermediate the folate-dependent remethylation branch handles. Adequate cysteine reduces demand on that branch and supports glutathione synthesis. The two therefore sit on the same node of one-carbon and sulfur metabolism. Homocysteine remains a marker rather than a clinical outcome.

Levomefolate + Vitamin B1 (thiamine)Established co-formulation in B-complex products

Thiamine appears with active folate in B-complex formulas and has its own role as thiamine pyrophosphate in decarboxylation reactions. It has no direct step in the folate cycle. The pairing reflects the B-complex convention rather than a shared reaction. Regard it as formulation practice.
Who should be cautious

Nothing specific on file for Levomefolate. Match the label to the daily amount above, and tell your doctor what you take.

Not medical advice. Show the label to your pharmacist.

What Levomefolate actually does.

Established

Levomefolate is the same folate form that already circulates in human blood.

3 more mechanisms
Established

Folic acid needs several conversion steps in the body first, while levomefolate arrives already converted.

Established

It hands a methyl group to an enzyme that turns homocysteine back into methionine, and that enzyme needs B12 to work.

Established

If B12 is short, folate gets stuck in the methyl form and cannot be recycled into the other folate jobs.

Made in a lab, 6 steps on record

Where Levomefolate comes from.

It is built step by step in a chemical plant, then the one mirror-image form the body uses is separated out and locked into a stable salt, because the pure active form falls apart in air.

What this route gives you

Chemically synthesised. The molecule is identical to the one a plant or an animal makes, and building it deliberately means a known purity, a fixed dose and no crop contaminants. For several nutrients this is the only route that reaches a usable amount.

6 steps on record
Starts as
Petrochemical and fine chemical intermediates

The synthesis starts from commodity aromatic and heterocyclic intermediates, including a pterin precursor and a glutamate unit, rather than from any plant or animal material.

Converted by
Pterin ring construction and coupling

The pteridine ring is assembled and coupled through a para-aminobenzoyl unit to L-glutamic acid, giving the folate skeleton.

Converted by
Reduction and methylation

The folate is reduced to the tetrahydro state and methylated at N5. Reduction creates a new stereocentre at C6, producing a mixture of the (6R) and (6S) forms.

Purified by
Resolution of the (6S) isomer

The diastereomers are separated, typically by fractional crystallisation with a chiral resolving agent, to isolate the (6S) form that human folate enzymes and transporters use. This step is what distinguishes the commercial active from racemic material.

Ends up as
Salt formation and crystallisation

The resolved acid is converted to its calcium or glucosamine salt and crystallised, because the free reduced folate is unstable to oxygen and moisture.

Standardised to
Assay, isomeric purity and packaging

Material is assayed by HPLC for potency and for (6S) isomeric purity, then packed under inert gas with desiccant to hold that purity through shelf life.

Getting Levomefolate from food.

The whole-food sources on file. A supplement closes the gap, it does not replace dinner.

Lentils (cooked)Spinach (cooked)Asparagus (cooked)

A gram-for-gram figure (how much of each you would eat to match a dose) will appear here once it is sourced and reviewed. This page will not print a number it cannot cite.

The forms it comes in.

Calcium L-5-methyltetrahydrofolateThe (6S) diastereomer paired with calcium as counterion, supplied as a crystalline solid, with published stability data behind it.Fits Solid dose forms where a defined crystalline salt with established stability data suits the process.Trade-off Water solubility is limited relative to the amine salts, and the calcium counterion contributes a small amount of calcium that a formula may need to account for.
3 more forms
(6S)-5-methyltetrahydrofolic acid glucosamine saltThe same (6S) anion paired with glucosamine instead of calcium, giving higher aqueous solubility and a different crystal habit.Fits Liquids, sachets and formulas where solubility drives the choice.Trade-off The counterion is derived from a shellfish-associated raw material in some supply chains, which matters for declaration and for people avoiding it.
L-5-methyltetrahydrofolic acidThe unsalted acid, chemically the same anion without a stabilising counterion.Fits Reference and analytical use, and formulations where an added counterion is unwanted.Trade-off It is markedly more prone to oxidation and moisture uptake than the salts, so it demands tighter packaging and handling controls.
Racemic 5-methyltetrahydrofolate (6R,6S mixture)A 50:50 mixture of the two diastereomers, of which only the (6S) form is the natural substrate for human folate enzymes and transporters.Fits Historic and analytical contexts. Supplement-grade material is normally the resolved (6S) form.Trade-off Half the mass is the (6R) form, which the folate enzymes do not use, so a stated weight overstates the usable amount unless the label specifies (6S).
What the strongest studies found

The essence, in one line each.

  1. Pooling trials in women of childbearing age, the active form of folate improved blood measures of folate status, including plasma and red blood cell folate, compared to folic acid.Meta-analysis. Xie et al., 2025 (Medicine). PMID 41398893 ↗
3 more findings
  1. In a 6-month randomised trial in healthy women of reproductive age, taking a folate-fortified oral contraceptive increased the proportion of women meeting benchmarks for adequate folate levels.Randomised trial. Castaño et al., 2014 (Public Health Nutrition). PMID 23534865 ↗
  2. In healthy women, a folate-supplemented oral contraceptive produced levomefolate blood exposure comparable to the same components taken separately.Randomised trial. Wiesinger et al., 2012 (Clinical Drug Investigation). PMID 22909145 ↗
  3. In a pilot study of adults with a diagnosed blood-sugar condition, a three-month multi-nutrient supplement containing L-methylfolate significantly reduced blood homocysteine levels.Open-label trial, in patients with diabetes. Schmidl et al., 2020 (Molecular Vision). PMID 32355442 ↗

Chosen from the 34 we read for Levomefolate.

Primary evidence

The studies, linked.

1 source behind our Levomefolate verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.

  1. ClinicalTrials.gov ↗

From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.

Side effects reported to the FDA

Problems people have reported.

Read this carefully. These are 93,778 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Levomefolate is, not how risky it is. A report is not proof Levomefolate caused anything. It is a signal of what to watch for, nothing more.

Fatigue
3,783
Nausea
3,327
Drug Ineffective
3,201
3 more reported effects
Diarrhoea
2,887
Headache
2,661
Dizziness
2,367

Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.

Every figure on this page, at source

Labs test. IngredientMD verifies.

Crider et al., 2019 (Nutrients)Meta-analysis. Time to effect, a median of about 36 weeks of daily intake.PMID 30609688
Sources checked 21 July 2026. A strength word says how much research stands behind a claim. It is never a product score.Educational information about an ingredient, not medical advice and not a claim about any specific product. Statements about ingredients have not been evaluated by the Food and Drug Administration. Bring the label to your pharmacist.

FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.