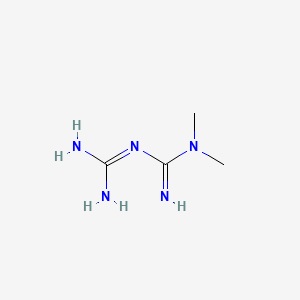
 Compound
- Category
- Compound
- Also filed under
- AMPK activationLongevity research
What Metformin is, and what it does.
- Does it work
- It is a prescription-only medicine, so who it suits is a decision for your prescriber. If you take it, the supplement question that matters is keeping vitamin B12 status topped up.
- How much to take
- This is a prescription-only medicine, so the daily amount is set by the prescribing clinician. Ongoing prescriptions sit around 500 to 1,500mg a day.
- Time to feel it
- Glucose readings move inside the first week or two, and most of the change lands by weeks four to eight. Digestive grumbling, where it happens, shows up first.
- The first dose
- Day one often means an unsettled or loose gut for a few hours, which comes from its action in the intestine. Glucose numbers have barely moved yet.
- With regular use
- Most effects take 2-8 weeks. Be patient.
- How well tolerated
- Generally well tolerated. Check with your doctor if on medications.
- How it feels
- Blood sugar stabilization. GI side effects common initially. Longevity effects not yet proven.
- The overlooked benefit
- Long-term use lowers vitamin B12 status in a fair share of people, and methylmalonic acid catches that earlier than serum B12 does. Worth raising with your prescriber.
How long it takes.
Source: UKPDS, Lancet, 1998; Diabetes Prevention Program Research Group, 2002
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
- Hepatic glucose outputMeta-analysis
- Glucose metabolismMeta-analysis
4 more claims
- Vitamin B12 status during long-term useMeta-analysis
- AMPK activation through partial complex I inhibitionNarrative review
- Gut microbial composition and bile acid handlingRandomised trial
- Markers followed in ageing researchCohort study
Questions people ask about Metformin.
- When should I take it?
- Timing matters less than consistency. Pick a time that works for you and take it daily.
2 more questions
- Can I take it with other supplements?
- Usually fine. The main thing to watch is not doubling up on the same ingredient from different products. If you're on prescription meds, check with your pharmacist first.
- Any side effects to watch for?
- Most people tolerate it well at recommended doses. GI upset is the most common complaint with any supplement. Start with a lower dose and work up. If something feels off, stop and reassess.
Why these belong in the same formula, 23 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
Metformin interferes with the calcium dependent uptake of the intrinsic factor B12 complex at the ileal receptor. Long term use lowers circulating B12, which is why status is normally monitored.
The ileal receptor that binds the intrinsic factor B12 complex needs calcium, and metformin disturbs that calcium dependent membrane step. Supplemental calcium restores the uptake.
When B12 falls the folate cycle stalls at the methyl form and homocysteine rises. Active folate keeps that arm of the cycle supplied while B12 is being addressed.
Berberine inhibits mitochondrial complex I and activates AMPK, the same broad mechanism metformin uses. Effects on glucose handling and on gastrointestinal tolerance both add together.
Lipoic acid activates AMPK and promotes GLUT4 movement to the cell surface. It acts on the same signalling node from a different direction.
Inositol phosphoglycans act as second messengers downstream of the insulin receptor. Metformin acts mainly on hepatic glucose output, so the two work at different points of the same handling of blood sugar.
D-chiro-inositol supports the glycogen synthesis arm of insulin signalling inside the cell. That is downstream of where metformin acts, so the two are complementary.
Magnesium is required by the tyrosine kinase activity of the insulin receptor and by many ATP dependent steps. Adequate magnesium supports the same glucose handling metformin influences.
Deoxynojirimycin slows the intestinal breakdown of starch into absorbable glucose. That works before absorption, where metformin works after it, so the mechanisms do not overlap.
Viscous fibre delays gastric emptying and flattens the rate of glucose entering the blood after a meal. It also compounds the gastrointestinal fullness metformin can cause.
Gymnemic acids interfere with glucose transport across the intestinal wall and blunt sweet taste signalling. This acts on intake and absorption rather than on hepatic output.
Several 2026 trials tested multi-strain probiotics alongside metformin and reported fewer gastrointestinal complaints and changes in anthropometric and metabolic measures compared with metformin alone. Part of metformin's action runs through the gut microbiome and bile acid pool, which is the proposed point of contact. Anyone taking a prescribed medicine should have any addition reviewed by their prescriber.
A trial of Bifidobacterium animalis subsp. lactis BLa80 reported changes in glycaemic markers and gut microbiota composition in the supplemented group. Glycaemic markers are markers, not clinical outcomes. Strain-specific findings do not transfer to other bifidobacteria.
Saccharomyces boulardii has the widest evidence base of any probiotic for loose stools during medication courses. Metformin's most common early complaint is gastrointestinal, and bacterial multi-strain products have been tested for it directly. The extension to this yeast is reasoning by class rather than a tested pairing.
Homocysteine is remethylated either by methionine synthase, which needs vitamin B12 and 5-methyltetrahydrofolate, or by betaine homocysteine methyltransferase, which uses betaine. When the B12 dependent route is limited, the betaine route carries more of the load. That two-route arrangement is settled biochemistry and is why betaine appears in formulas built around methylation.
Metformin is a substrate for OCT1, OCT2 and the multidrug and toxin extrusion transporters, and thiamine moves through overlapping cation transport systems including THTR-2. Competition at a shared carrier is a recognised class of interaction. The clinical size of that competition in people has not been quantified, so read it as mechanistic.
A 2025 systematic review and meta-analysis assessed chromium supplementation in women, with metformin used as background care in several of the included trials, reporting effects on insulin and glucose indices. Those are markers rather than clinical outcomes. Because both point the same direction on glucose markers, the combination is additive rather than complementary, and additive glucose lowering in someone on prescribed medication is a conversation for the prescriber.
Metformin's primary molecular action is partial inhibition of complex I, which passes electrons to ubiquinone. Coenzyme Q10 is co-formulated on the reasoning that the downstream carrier supports the chain. No human study has shown that supplemental coenzyme Q10 changes anything about metformin's effect, so this is a mechanistic proposal.
Psyllium forms a gel that flattens the post-meal glucose curve, an effect reproduced across many trials, and the same gel can delay the absorption of medicines taken at the same time. Separating a viscous fibre from an oral medicine by a couple of hours is standard dispensing practice for that reason. Both directions of the interaction matter here.
A 2026 study reported that the prolactin-lowering effect of metformin differed by baseline vitamin D status in the participants studied. Prolactin is an endocrine marker, and the finding is an effect modification within one cohort rather than a demonstrated benefit of combining the two. It is worth flagging because vitamin D status is common background variation in anyone taking metformin.
Riboflavin becomes FMN, the flavin prosthetic group of complex I itself, and FAD for complex II and the acyl-CoA dehydrogenases. That cofactor requirement holds regardless of metformin. It is established biochemistry rather than an interaction finding.
Methionine synthase requires both 5-methyltetrahydrofolate as methyl donor and methylcobalamin as cofactor. When the cobalamin side is limited, folate becomes trapped as the methyl form and cannot re-enter other one-carbon reactions. That methyl folate trap is textbook biochemistry. It is why folate status alone does not describe the picture where B12 status is falling.
Zinc, iron and copper compete for shared divalent metal transport at the enterocyte, so mineral stacks affect one another regardless of any medicine present. This matters for anyone assembling a nutrient regimen around a prescription. The competition is established absorption pharmacology.
Nothing specific on file for Metformin. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Metformin actually does.
Metformin is a prescription drug, not a supplement ingredient, so anything taken alongside it should go through the prescribing clinician.
3 more mechanisms
It doesn't cross cell membranes on its own, it relies on specific transport proteins to get into liver cells and to be cleared unchanged by the kidneys, with the liver barely processing it at all.
Its main action is a partial slowdown of an energy-producing step inside cells, which shifts an internal energy signal and reduces the liver's glucose output.
Long-term use lowers vitamin B12 status in a good number of users, likely by interfering with how B12 binds its carrier protein for absorption in the gut.
Where Metformin comes from.
It is made in a chemical plant, not from a plant or an animal. Two simple industrial chemicals are heated together to build the molecule, which is then crystallised, purified, tested against a pharmacy standard and pressed into tablets or dissolved for a liquid.
What this route gives you
Chemically synthesised. The molecule is identical to the one a plant or an animal makes, and building it deliberately means a known purity, a fixed dose and no crop contaminants. For several nutrients this is the only route that reaches a usable amount.
5 steps on record
Both are commodity petrochemical and ammonia-derived intermediates. Dicyandiamide is made from calcium cyanamide, itself made from limestone and nitrogen.
Dimethylamine hydrochloride and dicyandiamide are heated together, and the amine adds across the cyanamide nitrile to form the biguanide skeleton directly as the hydrochloride salt.
Crude metformin hydrochloride is recrystallised from water or an alcohol-water system to remove unreacted starting materials and related biguanide impurities.
Release testing follows the pharmacopoeial monograph for assay, related substances and residual solvents. Nitrosamine impurity control has been a specific focus of regulatory testing for this molecule since 2019.
The salt is granulated with binders and compressed. Extended-release products embed it in a hydrophilic polymer matrix, most often hypromellose, that controls the release rate.
Getting Metformin from food.
The whole-food sources on file. A supplement closes the gap, it does not replace dinner.
A gram-for-gram figure (how much of each you would eat to match a dose) will appear here once it is sourced and reviewed. This page will not print a number it cannot cite.
The forms it comes in.
1 more form
The essence, in one line each.
- In a meta-analysis of six studies in women with a diagnosed hormonal condition, adding a probiotic to metformin improved insulin resistance and led to fewer gastrointestinal side effects compared to taking metformin alone.Meta-analysis, in women with polycystic ovary syndrome. Hamsho et al., 2026 (Frontiers in Endocrinology). PMID 41970993 ↗
5 more findings
- The review describes falling vitamin B12 status as a recognised and under-monitored consequence of long-term metformin use and argues for periodic status checks.Narrative review. Saini et al., 2026 (Acta Diabetologica). PMID 41961093 ↗
- In a 6-month clinical trial in 70 men with a diagnosed blood sugar condition and high prolactin levels from medication, taking 3 grams of metformin daily lowered prolactin levels only in those with sufficient vitamin D, not in those with vitamin D deficiency.Clinical trial (non-randomised), in adult men with antipsychotic-induced hyperprolactinemia and type 2 diabetes or prediabetes. Krysiak et al., 2026 (Nutrients). PMID 41978113 ↗
- Metformin altered signalling in the hypothalamic paraventricular and arcuate nuclei in the animal model used, offering a central mechanism alongside the hepatic one.Animal study. Yu et al., 2022 (Toxicology and Applied Pharmacology). PMID 35085591 ↗
- Reduced motility of the cultured cell line under metformin tracked with NAD+ depletion rather than with AMPK activation, pointing to an AMPK-independent action in that model.In vitro study. Cabrera et al., 2026 (Scientific Reports). PMID 42414524 ↗
- Silk-derived sericin changed how heterotypic cell spheroids formed and how they responded to metformin in the laboratory model.In vitro study. Calvo-Chica et al., 2026 (Biomaterials Advances). PMID 42335554 ↗
Chosen from the 12 we read for Metformin.
The studies, linked.
12 sources behind our Metformin verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Clinical trialRepaglinide and Metformin Combination Tablet (NN4440) in a TID Regimen Compared to a BID Regimen and BID Avandamet in Subjects With Type 2 Diabetes: A Twenty-Six Week, Open-Label, Multicenter, Randomized, Parallel Group Trial to Investigate Efficacy and SafetyClinicalTrials.gov ↗Phase 3, 560 participants, Completed
11 more linked trials
- Clinical trialThe Effect of Metformin Versus Placebo, Including Three Insulin-Analogue Regimens With Variating Postprandial Glucose Regulation, on CIMT in T2DM Patients - A Randomized, Multicenter TrialClinicalTrials.gov ↗Phase 4, 415 participants, Completed
- Clinical trialA Prospective, Multi-centric, Open-label, Single-arm, Phase 4 Study to Evaluate the Safety and Efficacy of Canagliflozin + Metformin Hydrochloride IR Fixed-dose Combination as an Adjunct to Diet and Exercise to Improve Glycemic Control in Indian Adult Patients With Type 2 Diabetes Mellitus When Treatment With Both Canagliflozin and Metformin is AppropriateClinicalTrials.gov ↗Phase 4, 276 participants, Completed
- Clinical trialA Phase 2b, Randomized, Double-Blind, Parallel-Group, Study of Safety and Efficacy of 16 Weeks of Treatment With DIO-902 or DIO-902 Placebo in Addition to Metformin and Atorvastatin or Atorvastatin Placebo in Subjects With Type 2 Diabetes Mellitus (Protocol No. DIO-502)ClinicalTrials.gov ↗Phase 2, 200 participants, Terminated
- Clinical trialEfficacy and Safety of Adjuvant Metformin for Operable Breast Cancer PatientsClinicalTrials.gov ↗Phase 2, 105 participants, Completed
- Clinical trialCOMPARATIVE EVALUATION OF SUBGINGIVALLY DELIVERED 1% METFORMIN AND ALOE VERA GEL IN TREATMENT OF INTRABODY DEFECTS IN CHRONIC PERIODONTITIS SUBJECTS: A RANDOMIZED CONTROLLED CLINICAL TRIALClinicalTrials.gov ↗Phase 2, 90 participants, Completed
- Clinical trialA Randomized Phase II Study of Chemotherapy ± Metformin in Metastatic Pancreatic CancerClinicalTrials.gov ↗Phase 2, 60 participants, Terminated
- Clinical trialRandomized, Non-blinded Crossover Study to Establish the Bioequivalence Between Fixed Dose Combination (FDC) and Loose Combination of Acarbose and Metformin and to Investigate the Potential for a Drug-drug Interaction Following Single Oral Dosing in Healthy Adult Male SubjectsClinicalTrials.gov ↗Phase 1, 40 participants, Completed
- Clinical trialA Double-Blind, Placebo-Controlled Trial of Anti-Aging, Pro-Autophagy Effects of Metformin in Adults With PrediabetesClinicalTrials.gov ↗Phase 3, 25 participants, Completed
- Clinical trialEffects of the PPAR-gamma Agonist Pioglitazone on Renal and Hormonal Responses to Salt in Diabetic and Hypertensive SubjectsClinicalTrials.gov ↗Phase 4, 16 participants, Completed
- Clinical trialA Phase I, Open-label, Single-center Study to Assess the Pharmacokinetics of Metformin, an OCT2 Substrate, in Healthy Subjects When Administered Alone and in Combination With a Single Oral Dose of Vandetanib (CAPRELSA) 800 mgClinicalTrials.gov ↗Phase 1, 14 participants, Completed
- Clinical trialEffects of GLP-1 Receptor Agonists Combined with Metformin and Healthy Lifestyle Education Prior to Fertility Treatment on Reproductive Outcomes in Women with PCOS and ObesityClinicalTrials.gov ↗392 participants, Not yet recruiting
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 841,175 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Metformin is, not how risky it is. A report is not proof Metformin caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.