Cannabidiol.
Research-backed compound with potential health benefits. Reduces anxiety, improves sleep quality, and can help with certain types of chronic pain. It works with your body's endocannabinoid system to bring things back to balance.
Reviewed March 2026
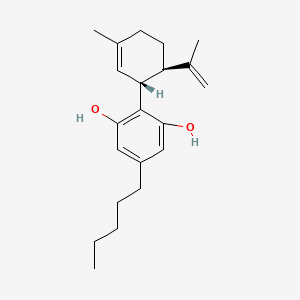 Compound
- Category
- Compound
What Cannabidiol is, and what it does.
- Does it work
- Yes, for specific goals. If you struggle with anxiety or sleep, it's worth a shot. Less proven for general 'wellness'.
- How much to take
- Start low, go slow. 25-50mg per day is a good starting point. Some studies use 300-600mg for social anxiety. Highly individual.
- Time to feel it
- Taken as an oil with food, blood levels peak in one to three hours. Most people describe a steadier baseline over two to four weeks of daily use rather than on day one.
- The first dose
- Maybe a slight sense of calm if you take a higher dose, but for many, nothing.
- With regular use
- After 2-4 weeks, many people report a noticeable decrease in baseline anxiety. Better sleep patterns. It helps regulate, not sedate.
- How well tolerated
- Generally well tolerated. The main risk is interaction with other medications. The biggest issue is buying a sketchy product with contaminants or no actual CBD.
- How it feels
- A gentle easing of tension. Like turning the volume down on stress. Not intoxicating or sedating, just... calmer.
- The overlooked benefit
- Blood levels come out several times higher when it is taken with a fat-containing meal than on an empty stomach, so when you take it changes exposure as much as how much you take.
How long it takes.
Source: Millar et al. (2019) Front Pharmacol dose review; Epidiolex prescribing data
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
Cannabidiol is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.
- self-rated calm during a public speaking taskRandomised trial
- sleep quality ratings with evening dosingRandomised trial
4 more claims
- increase in oral absorption with a fat-containing mealRandomised trial
- inhibition of cytochrome P450 enzymes that clear many medicinesIn vitro study
- muscle soreness ratings after hard trainingRandomised trial
- negative allosteric modulation at CB1 and activity at TRPV1 and 5-HT1AIn vitro study
Questions people ask about Cannabidiol.
- Will this make me high?
- No. It's non-psychoactive. THC is the compound in cannabis that gets you high. Reputable products have less than 0.3% THC.
5 more questions
- Is it legal?
- Federally legal in the US if it's from hemp and has <0.3% THC. Some state laws differ, so it's smart to double-check locally.
- Full-spectrum, broad-spectrum, or isolate?
- Start with full-spectrum. It contains other plant compounds that create an 'entourage effect', which seems to make it more effective for many.
- Will I fail a drug test?
- It's possible. Full-spectrum has trace amounts of THC that could build up. If you're tested for work, use a 'THC-free' broad-spectrum or isolate to be safe.
- What's the best time to take it?
- Depends on your goal. For sleep, an hour before bed. For general anxiety, a morning dose or splitting it between morning and night works well.
- How long until it works?
- Tinctures under the tongue can have a calming effect in 15-45 minutes. For lasting benefits like better sleep, give it 1-2 weeks of consistent use.
Why these belong in the same formula, 13 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
Cannabidiol dissolves in lipid, not water, so a medium-chain triglyceride carrier keeps it in solution through the gut lumen and into mixed micelles. Most consumer tinctures are formulated in MCT for exactly this reason. The effect is on how much reaches circulation, an absorption parameter rather than an outcome.
Long-chain fats stimulate bile release and chylomicron formation, and lipophilic cannabinoids partition into that stream. Co-dosing with an oil-based omega-3 softgel is a practical way to take cannabidiol with fat. This concerns uptake, not any clinical endpoint.
Piperine slows first-pass metabolism broadly, so a piperine-containing formula can raise cannabinoid exposure beyond what the label dose suggests. That cuts both ways and is worth flagging rather than selling. Anyone taking medicines cleared by CYP3A4 or CYP2C19 should raise the combination with a clinician.
Curcumin and cannabidiol are commonly stacked in the same oil base and share a metabolic bottleneck. The interaction is pharmacokinetic, affecting blood levels rather than any measured endpoint. Read it as mechanistic rather than clinical.
Sustained St Johns wort intake pushes hepatic and intestinal CYP3A4 upward, and cannabidiol is metabolised through that isoform. The expected direction is lower cannabidiol exposure at the same dose. This is an anti-synergy and belongs on a caution list, not a stack card.
Night-time cannabidiol products routinely carry melatonin, and both can add to next-morning grogginess in sensitive users. No combination trial supports a specific joint dose. The pairing is formulation convention with a plausible additive direction.
Valerian acts on GABAergic tone and cannabidiol has its own calming profile, so the combined effect on alertness can exceed either alone. Driving and machinery caution applies. The additive direction is the claim, not a magnitude.
Chamomile apigenin binds benzodiazepine-site receptors in laboratory work, and the two show up together in sleep formulations. Nothing has measured the pair in people. Confidence stays low on purpose.
L-theanine raises alpha-band cortical activity and modulates glutamate and GABA signalling. Cannabidiol works through a separate, non-CB1-agonist profile. Non-overlapping targets are why they are formulated together. No trial has tested the combination.
Caffeine raises arousal while cannabidiol is used to settle it, so the two pull against each other in the same product. Some users report the pairing smooths caffeine jitter, which is subjective and unmeasured here. Flagged as an opposing-direction combination rather than a benefit.
Cannabinoids oxidise on exposure to air and light, and a tocopherol in the carrier oil delays that loss. The role is shelf stability of the oil, nothing physiological. Vitamin E acetate in vape products is a separate matter and not what an oral oil uses.
The in vitro inhibition is well described. How much it moves cannabidiol levels in a person is not established. Flagged so a formulator knows the overlap exists. Read it as mechanistic.
Ashwagandha acts on the hypothalamic-pituitary-adrenal axis while cannabidiol does not. Products pair them for a stress-support positioning. Nothing has measured the two together.
Nothing specific on file for Cannabidiol. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Cannabidiol actually does.
CBD is very fat-loving and doesn't dissolve well in water, so how much you absorb from an oral dose depends on dietary fat and bile to help it along.
3 more mechanisms
CBD goes through heavy processing by the liver on its first pass through, so how much reaches your bloodstream from an oral dose is generally low and varies a lot from person to person.
In lab studies, CBD blocks several liver enzymes that break down other substances, which is the basis for its known potential to change how fast co-taken medications get cleared.
Unlike THC, CBD doesn't directly switch on the CB1 receptor, it instead dampens it and also acts on other targets that aren't cannabinoid receptors, including certain heat- and serotonin-sensing pathways.
Where Cannabidiol comes from.
It starts as dried hemp. A solvent pulls out the oily fraction, heat converts the plant acid into cannabidiol, and further cleanup decides whether the finished material keeps the rest of the plant, has the THC taken out, or ends up as pure white powder.
What this route gives you
Made from a plant. What ends up in the capsule tracks the harvest, so batch testing and a stated marker matter more here than with a made molecule.
6 steps on record
Flower and leaf of Cannabis sativa cultivars bred for high cannabidiol and low tetrahydrocannabinol, harvested and dried to a stable moisture level.
Supercritical carbon dioxide or food-grade ethanol pulls the cannabinoid and terpene fraction from the milled biomass. Carbon dioxide runs cold and leaves no residual solvent to remove. Ethanol is faster and cheaper per kilo but co-extracts more chlorophyll and waxes.
Controlled heating converts cannabidiolic acid to cannabidiol. Time and temperature set how complete the conversion is, and raw-profile products deliberately stop short.
Chilling in ethanol drops out waxes and lipids, then short-path or wiped-film distillation concentrates the cannabinoid fraction into a distillate.
Chromatography removes tetrahydrocannabinol to give a broad-spectrum fraction, or crystallisation from a solvent gives isolate. Full-spectrum material skips this step.
Distillate or isolate is dosed into an MCT or hemp seed oil carrier, blended onto a powder carrier, or nanoemulsified for aqueous formats, with a third-party certificate of analysis for cannabinoid content and contaminants.
The forms it comes in.
3 more forms
The essence, in one line each.
- In a systematic review of 4 randomised trials in 120 adults, oral cannabidiol was associated with lower blood pressure, with all four studies reporting significant reductions in systolic blood pressure compared to a placebo, particularly under stress or during sleep.Systematic review. Roberts et al., 2026 (Journal of cannabis research). PMID 42321899 ↗
12 more findings
- In a meta-analysis of human trials, cannabidiol was not associated with a significant change in several circulating inflammatory markers, with effects that were inconsistent between studies and often trivial.Meta-analysis. Candeloro et al., 2025 (International journal of molecular sciences). PMID 41373770 ↗
- In a systematic review of studies in healthy, physically active people, cannabidiol showed a limited beneficial effect on some physiological measures like VO2 and power, but there was limited evidence for its effects on strength or recovery after exercise.Systematic review. Bezuglov et al., 2024 (Nutrients). PMID 39275158 ↗
- Over eight weeks in healthy younger adults, daily cannabidiol was associated with better self-reported sleep quality and higher natural killer cell activity than a placebo.Randomised trial. Kisiolek et al., 2023 (Nutrients). PMID 37836465 ↗
- In healthy, well-trained people, a single dose of cannabidiol after intensive resistance training was linked to small but significant group differences in muscle damage markers and squat performance recovery after 72 hours.Randomised trial. Isenmann et al., 2021 (Nutrients). PMID 34578906 ↗
- A broad-spectrum cannabidiol supplement did not produce a detectable difference in 10-minute cycle ergometer performance, which is a failure to detect an effect rather than evidence that none exists.Randomised trial. Gillham et al., 2024 (European Journal of Sport Science). PMID 38956805 ↗
- In a 10-week trial, daily use of a broad-spectrum cannabidiol supplement by healthy adults led to detectable levels of other cannabinoids in their urine, which increased after a bout of exercise.Randomised trial. Gillham et al., 2026 (Medicine and Science in Sports and Exercise). PMID 40920736 ↗
- Long-term cannabidiol supplementation was tolerated in healthy adult dogs over the study period, with the report describing tolerability rather than any efficacy endpoint.Animal study. Corsato Alvarenga et al., 2024 (Journal of Veterinary Internal Medicine). PMID 38009749 ↗
- Dietary cannabidiol was assessed against growth performance, behaviour, blood profile and metabolomic measures in a livestock feeding trial. The readouts are markers, not human outcomes.Animal study. Addeo et al., 2025 (Veterinary Sciences). PMID 40905739 ↗
- Hemp-derived cannabidiol supplementation was measured against blood variables, carcass characteristics and meat quality in a non-human feeding study.Animal study. Tathong et al., 2024 (Animals). PMID 38929337 ↗
- In a rodent model, high-intensity interval training with cannabidiol supplementation altered cognition-related measures and associated signalling markers. These are mechanistic markers in animals, not human outcomes.Animal study. Kordi et al., 2024 (Iranian Journal of Basic Medical Sciences). PMID 39539449 ↗
- Cannabidiol supplementation shifted lipid precursors of inflammatory signalling in a model of elevated liver fat. The endpoints are lipid intermediates measured in tissue, not clinical outcomes.Animal study. Konstantynowicz-Nowicka et al., 2026 (Journal of Cannabis Research). PMID 41742322 ↗
- Cannabidiol-rich hemp oil given alongside doxorubicin was assessed for tolerability and for changes in doxorubicin pharmacokinetics in dogs, which flags a drug-exposure interaction worth knowing about.Animal study. Lejeune et al., 2025 (Journal of Veterinary Internal Medicine). PMID 40622742 ↗
Chosen from the 1,476 we read for Cannabidiol.
The studies, linked.
12 sources behind our Cannabidiol verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Clinical trialPlacebo-Controlled, Triple-Blind, Randomized Crossover Pilot Study of the Safety and Efficacy of Four Different Potencies of Smoked Marijuana in 76 Veterans With Chronic, Treatment-Resistant Posttraumatic Stress Disorder (PTSD)ClinicalTrials.gov ↗Phase 2, 80 participants, Completed
11 more linked trials
- Clinical trialRandomized, Double Blind, Placebo-Controlled Trial to Evaluate the Safety and Tolerability of Cannabidiol (CBD) in Moderate to Severe Rheumatoid ArthritisClinicalTrials.gov ↗Phase 1, 67 participants, Completed
- Clinical trialHome-based Quadriceps Isometric Exercise as a First-Line Rehabilitation Strategy for Knee Osteoarthritis Pain in Community-Dwelling Older Adults: A Randomized Factorial Pilot TrialClinicalTrials.gov ↗50 participants, Completed
- Clinical trialInfluence of Cannabidiol on Glucose Tolerance and The Gut MicrobiotaClinicalTrials.gov ↗30 participants, Completed
- Clinical trialThe Impact of Different Concentrations of Hemp-Derived Cannabidiol (CBD) Full-spectrum Oil Solutions in the Treatment of Depressive and Anxiety Disorders in Parkinson's Disease Patients.ClinicalTrials.gov ↗Phase 2, 27 participants, Completed
- Clinical trialA Phase I Exploratory Study to Assess the Pharmacokinetics of Single Inhaled Dose of Cannabis (Delta-9-Tetrahydrocannabinol / Cannabidiol) Administered by Vaporization Using a 4-Day Dose Titration In Healthy Male And Female VolunteersClinicalTrials.gov ↗Phase 1, 12 participants, Completed
- Clinical trialEffects of an Acute 1-month Cannabidiol Treatment on Pain and Inflammation After a Long Bone Fracture: a Triple-blind Randomized, Placebo Controlled Clinical TrialClinicalTrials.gov ↗Phase 2, 225 participants, Recruiting
- Clinical trialSex Differences in the Interface Between Cannabis Use and Stress Among Emerging AdultsClinicalTrials.gov ↗Phase 1, 148 participants, Recruiting
- Clinical trialEvaluation of the Effects of Isolated Cannabidiol (CBD) on Inflammation, Pain, Sleep and Quality of Life in Brazilian Jiu-Jitsu Athletes: A Randomized, Double-Blind, Placebo-Controlled Clinical TrialClinicalTrials.gov ↗Phase 2, 100 participants, Not yet recruiting
- Clinical trialEffects of Cannabidiol on Burnout Syndrome and Empathy of Paid and Unpaid Caregivers of Older AdultsClinicalTrials.gov ↗Early phase 1, 26 participants, Not yet recruiting
- Clinical trialCannabidiol for the Treatment of Diabetic Peripheral Neuropathy: Pilot StudyClinicalTrials.gov ↗Phase 1, 20 participants, Recruiting
- Clinical trialCannabidiol for the Treatment of Severe (Grades III/IV) Acute Graft-versus-host DiseaseClinicalTrials.gov ↗Phase 2, 10 participants, Unknown
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 47,013 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Cannabidiol is, not how risky it is. A report is not proof Cannabidiol caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.