Dehydroepiandrosterone.
Research-backed compound with potential health benefits. It's a building block for other hormones like testosterone and estrogen. As your natural levels drop with age, supplementing aims to restore some of that balance for mood, energy, and libido.
Reviewed March 2026
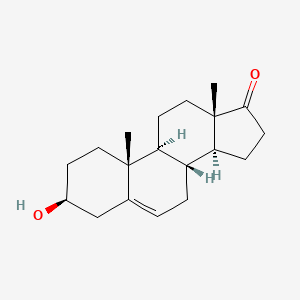 Compound
- Category
- Compound
- Also called
- Dehydroepiandrosterone
What Dehydroepiandrosterone is, and what it does.
- Does it work
- Suits adults past fifty with a measured low DHEA sulfate who are working with a clinician. It is a hormone precursor, so it belongs in that supervised setting.
- How much to take
- Start low. 25-50mg per day, taken in the morning. Don't just grab a 100mg pill because the bottle says so. More is not better here and just increases side effect risk.
- Time to feel it
- Blood DHEA sulfate rises within days of the first dose. Anything subjective takes four to eight weeks when it comes, and reports vary widely between people.
- The first dose
- Nothing. This is a hormone that needs to build and convert. Don't expect to feel anything for at least a few weeks.
- With regular use
- After 1-2 months, some users report better mood, deeper sleep, and improved libido. Effects are highly individual and often subtle.
- How well tolerated
- It's a hormone, so it needs respect. Not for anyone under 18 or with hormone-sensitive health issues. Talk to a doctor.
- How it feels
- Subtle, if anything. More like a background hum of well-being for some. It's not a stimulant. You're not supposed to 'feel' it kick in.
- The overlooked benefit
- Aromatase converts part of any dose into oestrogens, so it raises oestrogen exposure alongside androgens. Most men taking it for androgen reasons do not expect that.
25 to 50mg a day is where Dehydroepiandrosterone works.
Source: Rutkowski et al., Eur J Clin Invest, 2014; multiple RCTs
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
Dehydroepiandrosterone is documented in the library. The clinical read is in the queue. Nothing about the strength of the research prints until the read is done.
- Raising circulating DHEA sulfate toward younger adult levelsRandomised trial
- Bone mineral density in older adultsMeta-analysis
5 more claims
- Ovarian response in assisted reproductionMeta-analysis
- Testosterone already in the normal range in older menRandomised trial
- Skin hydration and thickness in older adultsRandomised trial
- Mood steadiness and wellbeing scoresRandomised trial
- Lean mass and body composition in older adultsMeta-analysis
Questions people ask about Dehydroepiandrosterone.
- Is DHEA a steroid?
- Technically, yes. It's a prohormone, which means it's a precursor to sex hormones like testosterone and estrogen. That's why you need to be careful with it.
4 more questions
- Who should take DHEA?
- Primarily adults over 40-50 who have low DHEA levels confirmed by a blood test. It's not for bodybuilders or young people looking for a shortcut.
- Will it make my hair fall out?
- It can. DHEA can convert to DHT, a hormone linked to hair loss in people who are genetically predisposed. If you notice thinning, stop taking it.
- Should I take it in the morning or at night?
- Morning. Your body's natural DHEA production is highest in the morning. Taking it then mimics your natural rhythm.
- Do I need to cycle DHEA?
- It's a good idea. Many doctors recommend taking it for a few months and then taking a break to reassess. This isn't a 'forever' supplement.
Why these belong in the same formula, 22 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
Pregnenolone is converted by CYP17A1 through 17-hydroxypregnenolone to DHEA, so it sits one enzymatic step upstream. Supplying both loads the same pathway at two points.
3-beta-hydroxysteroid dehydrogenase converts DHEA to androstenedione, the branch point toward both testosterone and oestrone. The two are consecutive members of one pathway.
17-beta-hydroxysteroid dehydrogenase reduces DHEA to androstenediol, which retains weak androgen receptor and oestrogen receptor activity of its own. It is one reduction step from the parent.
Androsterone arises from 5-alpha reduction and 3-alpha reduction of androgens derived from DHEA and is a major urinary end product of that pathway. It marks the disposal end of the same route.
Aromatase converts androstenedione, a direct DHEA metabolite, into oestrone. Chrysin is a flavone with aromatase-inhibiting activity in vitro, which is why it has long been co-formulated with DHEA, although its oral absorption is poor.
Part of a DHEA load is aromatised onward to oestrogens, which are then hydroxylated by CYP1A1 and CYP1B1. DIM shifts that hydroxylation balance, so it acts on the disposal side of the same pathway.
Steroid metabolites leave the body largely as glucuronide conjugates, and gut beta-glucuronidase can cleave those conjugates and return the steroid to circulation. Calcium D-glucarate yields glucaro-1,4-lactone, which inhibits that enzyme.
Pregnenolone branches either to progesterone through 3-beta-HSD or to DHEA through CYP17A1. The two arms draw on one precursor pool, so loading one branch changes what is available to the other.
Boron intake is associated with shifts in sex hormone binding globulin and in the free fraction of circulating steroids. That is an association with how much of a DHEA-derived androgen is unbound, not with how much is made.
The adrenal cortex holds one of the highest ascorbate concentrations of any tissue in the body, and ascorbate is consumed during steroidogenesis in the zona reticularis where DHEA is made. This is settled physiology of the gland rather than a supplementation result. It explains why the two appear together in adrenal-support formulas, and it is not a claim that adding ascorbate raises circulating DHEA.
Pantothenic acid is the backbone of coenzyme A, and acetyl-CoA is the starting point of the cholesterol synthesis that feeds every steroid including DHEA. Without adequate coenzyme A the whole steroidogenic supply chain slows. The relationship is upstream and nutritional, not a dose-response effect on circulating DHEA.
The first committed step of steroidogenesis happens on the inner mitochondrial membrane, where cholesterol side-chain cleavage depends on electron flow through the respiratory chain that ubiquinone carries. Ovarian and adrenal steroid output is therefore tied to mitochondrial competence. Products aimed at ovarian reserve routinely stack the two on this reasoning.
Myo-inositol and DHEA are combined in products aimed at ovarian response, where inositol acts on insulin signalling in the granulosa cell and DHEA supplies androgen substrate. A trial in the candidate set links the ovarian response to DHEA with androgen receptor expression, which is the receptor side of the same axis. The two arms have not been compared head to head in the candidate literature.
A 2026 meta-analysis of vitamin D supplementation tracked endocrine and metabolic markers, with DHEA sulfate among the androgen markers reported. Vitamin D receptors are present in steroidogenic tissue, which supplies the mechanism. The relationship is a measured marker association, not a demonstration that one raises the other.
An open-label flaxseed intervention reported reproductive endocrine profiles that include DHEA sulfate among the androgen markers followed. Lignans influence sex hormone binding globulin, which changes the free fraction of circulating androgens. This is an open-label marker readout, so it carries no control comparison.
Melatonin accumulates in follicular fluid and buffers oxidative stress in the same microenvironment where DHEA is converted to testosterone and then aromatised. Ovarian-support protocols stack them for that complementary reason: one supplies substrate, the other protects the compartment. The pairing rests on mechanism and use, not on a combination trial in this candidate set.
Zinc is a structural and catalytic component of enzymes across the androgen pathway and of the androgen receptor zinc fingers that read the signal once DHEA has been converted downstream. Adequate zinc status is therefore a precondition for the pathway operating normally. It is a permissive nutrient relationship, not an additive hormonal effect.
Every ATP-dependent step in the sulfation and desulfation cycle that stores DHEA as DHEA sulfate requires magnesium as the counter-ion of ATP. Sulfotransferase activity is nucleotide-dependent for that reason. This is background biochemistry rather than a supplementation interaction.
The sulfate group that converts DHEA to its circulating sulfated reservoir comes from PAPS, which is generated from inorganic sulfate produced by the molybdenum-dependent enzyme sulfite oxidase. Sulfur amino acid turnover therefore sits upstream of DHEA sulfate. The link is metabolic and does not imply that supplementing molybdenum changes DHEA sulfate concentrations.
N-acetylcysteine feeds the cysteine pool that is oxidised to inorganic sulfate and then activated to PAPS, the universal sulfate donor used by SULT2A1 to make DHEA sulfate. Sulfation capacity is substrate-limited when sulfur supply is low. The relationship is upstream substrate supply, not a hormonal effect.
Glycyrrhizin and its metabolite inhibit 11-beta-hydroxysteroid dehydrogenase type 2, which changes how the body handles cortisol and, with it, the mineralocorticoid balance that sits alongside adrenal androgen output. Combining a steroid precursor with an agent that alters steroid enzyme handling is a real pharmacological interaction. It is flagged as a caution for formulators, not as a benefit.
Ashwagandha is combined with DHEA in products aimed at the hypothalamic-pituitary-adrenal axis, where the botanical is studied for cortisol readouts and DHEA supplies steroid precursor. The two act at different points of the same axis. No combination trial exists in the candidate set, so the pairing is formulation logic.
Nothing specific on file for Dehydroepiandrosterone. Match the label to the daily amount above, and tell your doctor what you take.
Not medical advice. Show the label to your pharmacist.What Dehydroepiandrosterone actually does.
DHEA is made in the adrenal glands from cholesterol through a series of enzyme steps.
3 more mechanisms
Most DHEA in the blood is stored as a sulfate form that acts like a slow-release reservoir, and tissues convert it back to active DHEA as needed.
DHEA itself doesn't do much directly, it's a raw material that different tissues convert locally into a stronger androgen or into estrogens, depending on which enzymes that tissue has.
Blood DHEA levels peak in your twenties and decline steadily with age, one of the most consistent aging patterns known in hormone science.
Where Dehydroepiandrosterone comes from.
DHEA is made in a factory, not harvested. It starts from a compound in wild yam or soy, which chemists then rebuild step by step into the same molecule the adrenal glands make. The finished powder is identical whichever plant it started from. The human body cannot do this conversion, so a wild yam extract on its own does not give you DHEA.
What this route gives you
Chemically synthesised. The molecule is identical to the one a plant or an animal makes, and building it deliberately means a known purity, a fixed dose and no crop contaminants. For several nutrients this is the only route that reaches a usable amount.
6 steps on record
Saponins are extracted from wild yam tubers and hydrolysed to the sapogenin diosgenin. Some routes start instead from soy-derived stigmasterol or sitosterol.
The spiroketal side chain of diosgenin is opened and cleaved under acetic anhydride and acid conditions to give 16-dehydropregnenolone acetate, the classic intermediate of the steroid industry.
The 16-DPA intermediate is carried through oxidation and reduction steps that install the 17-ketone and the 3-beta-hydroxyl of dehydroepiandrosterone. Sterol-based routes instead use microbial side-chain cleavage to an androstenedione intermediate followed by chemical reduction.
The crude steroid is recrystallised from solvent to remove closely related steroid impurities, which is the step that determines the impurity profile of the finished powder.
HPLC assay against a reference standard sets the declared potency, with melting point and spectroscopy confirming identity. Related-substance limits are where residual synthetic intermediates are controlled.
The purified crystal is milled to a defined particle size and either blended into a dry dosage form or suspended in an oil fill.
The forms it comes in.
The essence, in one line each.
- Pooled trials of oral nutritional supplements, dehydroepiandrosterone among them, examined fertility measures in women with a reduced ovarian reserve.Meta-analysis, in women with diminished ovarian reserve (DOR). Li et al., 2025 (Annals of medicine). PMID 41185971 ↗
8 more findings
- In women with a diagnosed ovarian condition, taking DHEA for 8 weeks was associated with increased androgen receptor expression in ovarian cells, but did not significantly improve ovarian response or IVF outcomes compared to a control group.Cohort study, in diminished ovarian reserve women. Hu et al., 2017 (Journal of Ovarian Research). PMID 28472976 ↗
- In a randomised trial in 52 women with a diagnosed condition undergoing IVF, DHEA supplementation for at least 8 weeks was linked to a significantly higher live birth rate compared to a placebo.Randomised trial, in infertile women with normal ovarian reserve. Tartagni et al., 2015 (Minerva Ginecologica). PMID 24867068 ↗
- In a study of 122 infertile women with a diagnosed ovarian condition, taking 25 mg of DHEA three times a day for 12 weeks was associated with improved markers of ovarian reserve, an effect that was more evident in women younger than 38.Clinical trial (single-arm), in infertile women who had been diagnosed with DOR. Moslem Ahmad et al., 2024 (Steroids). PMID 39147007 ↗
- In women with a diagnosed poor response to ovarian stimulation, DHEA supplementation was associated with altered follicular fluid metabolome and cytokine profiles.Cross-sectional study, in poor ovarian responders. Viardot-Foucault et al., 2023 (Journal of Ovarian Research). PMID 37268990 ↗
- In a systematic review of 7 trials in women with a diagnosed eating disorder, dehydroepiandrosterone on its own did not improve bone mineral density compared to a placebo.Systematic review, in women with anorexia nervosa. Lin et al., 2022 (International Journal of Eating Disorders). PMID 35460091 ↗
- Protocol and design paper for a randomised investigation of DHEA supplementation. Describes the planned method rather than reporting an outcome.Study protocol. Bentley et al., 2021 (BMJ Open). PMID 34312190 ↗
- Correspondence responding to a report that DHEA supplementation showed no added benefit on live birth rate in poor ovarian responders. A failure to detect a difference is not evidence that none exists.Narrative review. Sethi et al., 2022 (BJOG). PMID 35373428 ↗
- DHEA supplementation produced tissue-specific and varying concentrations of dihydrotestosterone across compartments in male mice.Animal study. Colldén et al., 2022 (Endocrinology). PMID 36201601 ↗
Chosen from the 5,027 we read for Dehydroepiandrosterone.
The studies, linked.
9 sources behind our Dehydroepiandrosterone verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Clinical trialPolycystic Ovary Syndrome and Urinary Tract Stones: a BMI-Adjusted Analysis in Iraqi WomenClinicalTrials.gov ↗407 participants, Completed
8 more linked trials
- Clinical trialMulti-center, Double-blind, Placebo-controlled Study to Investigate the Efficacy and Safety of Daily Oral 100 mg Dehydroepiandrosterone (DHEA) Over 6 Treatment Cycles as a Concomitant Therapy to Oral Contraceptives (OC) to Alleviate Complaints of Reduced Libido in Women With Acquired Female Sexual Dysfunction (FSD) Associated With OC-useClinicalTrials.gov ↗Phase 2, 100 participants, Completed
- Clinical trialDouble-blind, Randomised, Placebo-controlled Phase III Study of Dehydroepiandrosterone (DHEA) in Respiratory Pulmonary Hypertension in AdultsClinicalTrials.gov ↗Phase 3, 60 participants, Completed
- Clinical trialCorrelation Between Dehydroepiandrosterone Sulfate and Sebum Level in Adult Female Acne VulgarisClinicalTrials.gov ↗50 participants, Completed
- Clinical trialGRACE-trial: a Randomized Active-controlled Trial for vulvovaGinal atRophy in breAst Cancer Patients on Endocrine Therapy.ClinicalTrials.gov ↗Phase 4, 31 participants, Completed
- Clinical trialDoes DHEA Improve Endothelial Dysfunction and Other Cardiovascular Risk Factors in Premenopausal Women With Systemic Lupus?ClinicalTrials.gov ↗Phase 2, 13 participants, Completed
- Clinical trialEffect of Dehydroepiandrosterone on Live Birth Rate in Subfertile Patients With Poor Ovarian RespondsClinicalTrials.gov ↗350 participants, Unknown
- Clinical trialEvaluation of Serum Adrenal Androgens Among Prepubertal and Pubertal Boys With Autism Spectrum DisorderClinicalTrials.gov ↗100 participants, Unknown
- Clinical trialDissecting the IMpact of 11-OXygenated and Classic Androgens on Skeletal Muscle Insulin Sensitivity (DIMOXIS)ClinicalTrials.gov ↗20 participants, Unknown
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 557 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Dehydroepiandrosterone is, not how risky it is. A report is not proof Dehydroepiandrosterone caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.