Vitamin D3 (cholecalciferol).
The sunshine vitamin your body actually prefers. Critical for bones, immunity, and mood. Essential for calcium absorption, bone mineralization, immune regulation, mood support, and gene expression in virtually every tissue.
Reviewed March 2026
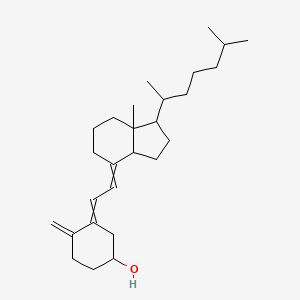 Vitamin
- Category
- Vitamin
- Also filed under
- Essential for calcium absorption and bone healthSupports immune functionSupports mood and mental healthReduces all cause mortality in deficient populations
What Vitamin D3 (Cholecalciferol) is, and what it does.
- Does it work
- Suits anyone with limited daylight, an indoor working life, or darker skin at high latitude. A blood level tells you where you are starting from and what a daily amount is holding.
- How much to take
- 1000-5000 IU daily depending on your baseline levels. Get a blood test (target: 40-60 ng/mL 25(OH)D). Each 1000 IU raises blood levels by roughly 10 ng/mL.
- Time to feel it
- Blood 25-hydroxyvitamin D rises across roughly eight to twelve weeks of daily use, then settles. A retest at three months is where the change becomes visible.
- The first dose
- Absorbed and begins metabolic processing in the liver. No noticeable effect yet.
- With regular use
- By 8-12 weeks, blood levels normalize. Bone density, immune function, and mood all improve in deficient individuals.
- How well tolerated
- Well tolerated at recommended doses. Toxicity is possible but requires extremely high doses (above 10,000 IU daily for extended periods). Always take with fat for absorption.
- How it feels
- If deficient: gradual improvement in mood, energy, and resilience to illness. If already sufficient: you likely won't feel a difference, which is fine.
- The overlooked benefit
- It needs bile and dietary fat to cross the gut wall, so the meal you pair it with changes how much gets in. The evening meal usually does that job well.
1,000 to 5,000 IU a day is where Vitamin D3 (Cholecalciferol) works.
Source: Holick 2017 meta-analysis + Endocrine Society
The proof, claim by claim.
What these words mean
These words describe the research, not the molecule's worth. Research strength is how much work stands behind one claim, and it is never a product score.
- Essential for bone health
- Improves mood
Questions people ask about Vitamin D3 (Cholecalciferol).
- How do I know if I'm deficient?
- Blood test for 25(OH)D. Below 20 ng/mL is deficient. Below 30 is insufficient. Aim for 40-60 ng/mL for optimal health.
5 more questions
- Should I take K2 with D3?
- It's a smart combo. D3 helps absorb calcium. K2 (specifically MK-7) helps direct that calcium to your bones instead of your arteries. They're complementary.
- Can I get enough from the sun?
- If you live below 35 degrees latitude, have light skin, and get 15-20 minutes of midday sun on large skin areas, maybe. Most people in modern life can't rely on sun alone.
- Can I take too much?
- Toxicity is rare but real at very high doses (above 10,000 IU daily for months). Symptoms include nausea, confusion, and kidney problems from elevated calcium. Stick to recommended doses.
- Why take it with fat?
- D3 is fat-soluble. Taking it with a fat-containing meal increases absorption by 50% or more. A handful of nuts or avocado works.
- Is the vegan D3 from lichen as good?
- Biochemically identical D3. Same molecule whether from lanolin or lichen. Lichen-sourced just costs a bit more.
Why these belong in the same formula, 19 pairings
Why these belong in the same formula. Each row says what the basis is, from settled biochemistry through to a trial that measured the pair.
The hydroxylases that convert cholecalciferol to 25-hydroxyvitamin D and then to calcitriol are magnesium-dependent, as is the transport protein. Vitamin D cannot be activated without adequate magnesium.
Vitamin D raises osteocalcin and matrix Gla protein output, and MK-7 carboxylates them so they can bind calcium and direct where it goes. Without K2 the induced proteins remain inactive.
Any menaquinone feeds the gamma-carboxylase that activates the Gla proteins vitamin D produces. The pairing is the standard mineral routing partnership.
Calcitriol induces the TRPV6 channel and calbindin that carry calcium across the intestinal wall. Vitamin D status sets how much of a calcium dose is absorbed.
The vitamin D receptor binds DNA as a heterodimer with the retinoid X receptor, so retinoid supply is part of the signalling machinery. Very high retinol intakes can also compete for that shared partner.
The vitamin D receptor uses zinc finger domains to bind its response elements. Zinc is structural to the receptor rather than to the vitamin.
Cholecalciferol needs dietary lipid to form the micelles it is absorbed in. An oil carrier or a meal raises uptake compared with a dry dose alone.
An omega-3 oil base supplies the long-chain fat that carries cholecalciferol into micelles, which is why softgels are usually oil-filled. The effect is on absorption, not on activation.
Ergocalciferol competes with cholecalciferol for vitamin D binding protein and 25-hydroxylase while producing a shorter-lived metabolite. Combining the two forms can lower measured 25-hydroxyvitamin D3.
Vitamin K1 feeds the same carboxylase and is partly converted to menaquinone-4 in tissues. It covers the carboxylation of vitamin D-induced Gla proteins from a second form.
Boron influences how the body handles calcium, magnesium and vitamin D metabolites, and the two are often formulated together in bone-support blends. The human data are limited and mostly report changes in circulating markers rather than structural outcomes. Regard this as a mechanistic pairing with modest supporting work.
Cholecalciferol is fat-soluble and needs bile salts to form the mixed micelles that carry it across the intestinal wall. Anyone with reduced bile flow absorbs less of any given dose. Supplemental bile components are used in that context, and the relationship is textbook physiology rather than a trial finding.
Phospholipid emulsifiers disperse cholecalciferol into fine droplets, which is the same physical step that micelle formation performs in the gut. This is why oil and phospholipid carriers appear in D3 softgels and emulsions. It is a delivery relationship, not an added biological effect.
Phosphatidylcholine is the specific phospholipid that does most of the emulsifying work in lecithin-based carriers. Cholecalciferol partitions into that lipid phase and is presented to the intestine already dispersed. The pairing addresses solubility, which is the main practical limit on a fat-soluble vitamin taken without food.
Bicarbonate and cholecalciferol were examined in the same body of intervention work, on the reasoning that acid load and vitamin D status both bear on muscle and mineral handling. The combination has been studied, not established. This row records that the pairing exists in the literature.
Carotenoids and cholecalciferol both rely on the same mixed micelles for uptake, and a large dose of one fat-soluble compound can occupy micellar capacity that another would use. The practical size of this competition varies with dose and meal fat. Flagged as a competition to be aware of rather than a reason to separate them.
Tocopherols travel the same micellar and lipoprotein route as cholecalciferol, so very large tocopherol doses share the same transport capacity. In a softgel they also protect the carrier oil from oxidation. Both directions of the relationship are worth stating and neither is a reason to avoid the pair.
A triglyceride carrier keeps cholecalciferol in solution and triggers the bile release that absorption depends on. Taking D3 with a fat-containing meal does the same thing without any special formulation. This is the simplest lever on absorption and it costs nothing.
The active hormone form of vitamin D raises intestinal uptake of both calcium and phosphate, and the two minerals are deposited together in bone mineral. Phosphate handling is also fed back on by FGF23, which suppresses activation of vitamin D. The pair is inseparable in normal mineral physiology.
Talk to a doctor before taking Vitamin D3 (Cholecalciferol) if any of these apply to you: Fat-soluble, so toxicity is possible at very high doses, Should be taken with fat for absorption, Get blood levels tested (target 40-60 ng/mL). These are flags to check first, not effects Vitamin D3 (Cholecalciferol) is known to cause.
Not medical advice. Show the label to your pharmacist.What Vitamin D3 (Cholecalciferol) actually does.
Vitamin D3 forms in your skin when UVB light hits a cholesterol-like molecule, which then reshapes itself with heat into the same D3 that a supplement gives you.
3 more mechanisms
Vitamin D3 on its own is not the active form. Your liver adds one chemical tag to make the storage form that blood tests measure, then your kidney adds a second tag to make the active hormone.
The active form attaches to a receptor inside cells that then changes how genes involved in calcium and phosphate handling get read.
Both steps that activate vitamin D rely on enzyme systems that need magnesium, which is the biochemical reason magnesium and vitamin D are often paired.
Where Vitamin D3 (Cholecalciferol) comes from.
Vitamin D3 is made by shining UVB light on a sterol taken either from sheep wool grease or from lichen, which is the same trick sunlight plays on your skin. The molecule that comes out is the same either way, and the source is what decides whether a product can call itself vegan.
What this route gives you
The same molecule is reached more than one way. Which route a given product used is a manufacturing choice, and the finished compound is the same either way.
7 steps on record
The animal route starts from wool grease recovered when raw wool is scoured. The vegan route starts from lichen biomass, either wild-collected or cultivated, which naturally contains the precursor sterol.
Cholesterol is separated from lanolin by saponification and solvent fractionation, or the sterol fraction is extracted from dried lichen.
Cholesterol is chemically dehydrogenated to 7-dehydrocholesterol, the same precursor human skin holds. In the lichen route the precursor is largely present already.
The precursor in solution is exposed to UVB light, which opens the B ring to previtamin D3. Controlled heating then completes the rearrangement to cholecalciferol. This is the industrial version of what sunlight does in skin.
The reaction mixture is separated by chromatography or crystallisation to remove tachysterol, lumisterol and unreacted precursor, giving crystalline vitamin D3.
The crystal is far too concentrated to handle directly, so it is diluted into oil or a dry carrier to a stated number of international units per gram and assayed.
The standardised concentrate is filled into softgels, sprayed into a dry matrix, or bottled as drops, usually with an antioxidant.
Many labels state lanolin or lichen because it affects vegan status, but the irradiation and purification steps are almost never described.
Getting Vitamin D3 (Cholecalciferol) from food.
The whole-food sources on file. A supplement closes the gap, it does not replace dinner.
A gram-for-gram figure (how much of each you would eat to match a dose) will appear here once it is sourced and reviewed. This page will not print a number it cannot cite.
The forms it comes in.
3 more forms
The essence, in one line each.
- In a systematic review and network meta-analysis of studies in adults with a diagnosed kidney condition, cholecalciferol was found to have potential advantages for increasing muscle mass.Systematic review, in patients with chronic kidney disease. Leng et al., 2026 (Frontiers in Nutrition). PMID 42027563 ↗
3 more findings
- In professional football players, a single high dose of vitamin D3 before a simulated match increased levels of vitamin D metabolites, with one form rising by 98% and another by 424%.Randomised trial. Ksiazek et al., 2026 (Nutrients). PMID 41515291 ↗
- In 315 adults who had received a kidney transplant, vitamin D3 levels showed no detectable correlation with kidney graft function or with any measures of body composition.Cohort study, in stable renal transplant recipients. Hryciuk et al., 2026 (International Journal of Molecular Sciences). PMID 42353105 ↗
- Vitamin D exposure altered decidualisation markers in cells recovered from menstrual effluent, a laboratory model finding rather than a clinical result.In vitro study. Metz et al., 2026 (The Journal of Clinical Endocrinology and Metabolism). PMID 41492807 ↗
Chosen from the 5 we read for Vitamin D3 (Cholecalciferol).
The studies, linked.
12 sources behind our Vitamin D3 (Cholecalciferol) verdict, every one linked to PubMed, the journal or ClinicalTrials.gov.
- Meta-analysisEfficacy of high-dose vitamin D in pediatric asthma: a systematic review and meta-analysisPubMed ↗Journal of Asthma, 2015, cited 63 times
11 more linked trials
- Meta-analysisNutritional vitamin D supplementation and health-related outcomes in hemodialysis patients: a protocol for a systematic review and meta-analysisPubMed ↗Systematic Reviews, 2015, cited 9 times, open access
- ReviewVitamin D Bioavailability: State of the ArtPubMed ↗Critical Reviews in Food Science and Nutrition, 2015, cited 330 times, open access
- ReviewScreening for Vitamin D Deficiency: A Systematic Review for the U.S. Preventive Services Task ForcePubMed ↗Annals of Internal Medicine, 2015, cited 125 times
- ReviewThe clinical use of vitamin D metabolites and their potential developments: a position statement from the European Society for Clinical and Economic Aspects of Osteoporosis and Osteoarthritis (ESCEO) and the International Osteoporosis Foundation (IOF)PubMed ↗Endocrine, 2015, cited 65 times
- ReviewHigh-Dose Vitamin D and Calcium Attenuates Bone Loss with Antiretroviral Therapy InitiationPubMed ↗Annals of internal medicine, 2015, cited 61 times, open access
- ReviewEffects of Supplemental Vitamin D and Calcium on Normal Colon Tissue and Circulating Biomarkers of Risk for Colorectal NeoplasmsPubMed ↗The Journal of steroid biochemistry and molecular biology, 2015, cited 52 times, open access
- ReviewVitamin D for the treatment of respiratory diseases: is it the end or just the beginning?PubMed ↗The Journal of steroid biochemistry and molecular biology, 2015, cited 52 times
- ReviewExtraskeletal Functions of Vitamin DPubMed ↗BioMed Research International, 2015, cited 15 times, open access
- StudyAdjunctive vitamin D for treatment of active tuberculosis in India: a randomised, double-blind, placebo-controlled trial.PubMed ↗The Lancet. Infectious diseases, 2015, cited 128 times
- StudyHigh-dose vitamin D3 in adults with pulmonary tuberculosis: a double-blind randomized controlled trial.PubMed ↗The American journal of clinical nutrition, 2015, cited 114 times, open access
- StudyProspective Evaluation of the Effect of Short-Term Oral Vitamin D Supplementation on Peripheral Neuropathy in Type 2 Diabetes MellitusPubMed ↗Medical Principles and Practice, 2015, cited 98 times, open access
From clinical trials and PubMed, ranked by study type and citation weight, not cherry-picked.
Problems people have reported.
Read this carefully. These are 190 voluntary, unverified reactions reported to the FDA (openFDA). The number mostly reflects how popular Vitamin D3 (Cholecalciferol) is, not how risky it is. A report is not proof Vitamin D3 (Cholecalciferol) caused anything. It is a signal of what to watch for, nothing more.
3 more reported effects
Source: openFDA adverse-event reports. Voluntary reporting, not an incidence rate.
FDA Disclaimer: These statements have not been evaluated by the Food and Drug Administration. This information is for educational purposes only and is not intended to diagnose, treat, cure, or prevent any disease. Consult your healthcare provider before starting any supplement regimen.